Every week, parents ask me about their child’s breathing, adults ask whether “airway orthodontics” can improve their health, and patients ask whether expanding the jaw will solve their sleep problems. Airway health has become one of the most common topics I discuss in practice.
Over the past few years, the conversation around airway-focused orthodontics has grown rapidly. Much of that discussion has been positive. It has increased awareness of the important relationship between jaw development, nasal breathing and sleep quality. Unfortunately, some clinicians have gone too far. They make claims that the evidence does not support, promise outcomes they cannot guarantee, recommend treatment without a proper diagnosis and blur the line between orthodontics and sleep medicine. Patients deserve better than that.
In this article, I share my evidence-based perspective on airway orthodontics. I explain what orthodontics can genuinely contribute to airway health, where the evidence is strong, where its limitations lie, and why orthodontists must work closely with ENT surgeons, sleep physicians and other medical specialists. In my view, multidisciplinary care is not optional—it is essential.
One of the most important messages I want parents and patients to understand is this: sleep-disordered breathing and airway obstruction often go unrecognised and undiagnosed.
This is not a controversial opinion, it is well established in the medical literature. For many years, clinicians believed that obstructive sleep apnoea (OSA) affected only 1–5% of children. More recent systematic reviews paint a different picture. Some studies report prevalence rates between 12.8% and 20.4% in young children, with rates increasing over the past decade. Adults face a similar problem. Most people with OSA remain undiagnosed despite living with the condition for years.
Why does this matter? Because untreated airway problems can have serious consequences. In children, sleep-disordered breathing can affect school performance, behaviour, attention, emotional wellbeing and physical development. In adults, it increases the risk of cardiovascular disease, metabolic disorders, excessive daytime sleepiness and a poorer quality of life.
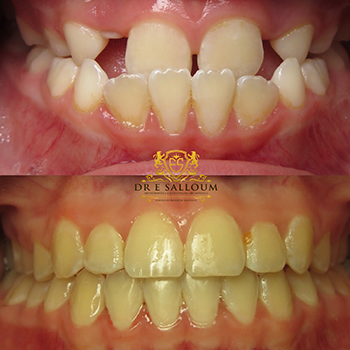
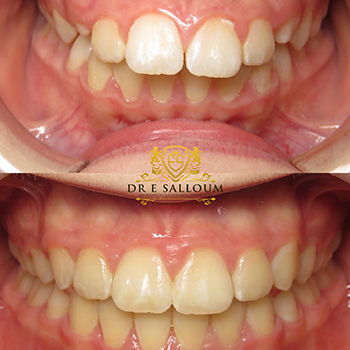
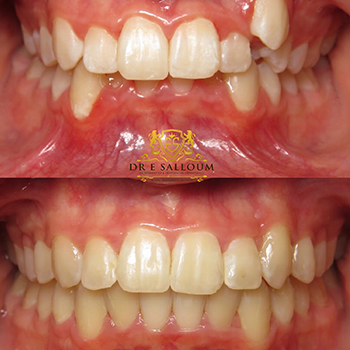
As a specialist orthodontist, I often identify signs that suggest a child may have an airway problem. I look for a narrow, high-vaulted palate, habitual mouth breathing, a long narrow facial pattern, snoring and restless sleep. These findings do not allow me to diagnose an airway disorder, nor do they mean that every child has one. However, they do tell me that I need to ask the right questions, discuss my concerns with the family and refer the child to the appropriate medical specialist for further assessment when indicated.
Orthodontists do not diagnose or treat sleep-disordered breathing. We screen for risk factors, recognise potential warning signs and work closely with ENT surgeons, sleep physicians and other medical colleagues. In my opinion, the greatest risk is not that we investigate too many patients, it is that we fail to recognise children and adults who genuinely need further assessment.
For adults, the apnoea-hypopnoea index (AHI) — the number of breathing interruptions per hour of sleep, measured during a formal sleep study (polysomnography or PSG) — is a reliable and well-validated measure for diagnosing and grading OSA.
In children, it is a different picture.
The British Thoracic Society (BTS) Guideline for Diagnosing and Monitoring Paediatric Sleep-Disordered Breathing (2023) makes clear that many diagnostic algorithms used in sleep studies, including the AHI, have not been validated in children. This is a critical point that parents and clinicians alike need to understand. A “normal” AHI result on a child’s sleep study does not rule out clinically significant sleep-disordered breathing.
The BTS guideline goes even further. It does not recommend routine polysomnography (a full sleep study) to diagnose sleep-disordered breathing in most children. Instead, clinicians should base the diagnosis on a thorough clinical assessment. This includes a detailed symptom history, validated questionnaires such as the Paediatric Sleep Questionnaire, a comprehensive clinical examination and, where appropriate, video or audio recordings of the child during sleep. In most paediatric cases, this information provides sufficient evidence to support a diagnosis and guide treatment decisions.
This is enormously important for families. If your child snores, breathes through their mouth, has restless sleep, wakes frequently, or grinds their teeth at night, these symptoms are clinically meaningful. They should not be dismissed because a sleep study came back within normal limits. The BTS guideline explicitly supports a symptom-led and observation-led approach in children, acknowledging the limitations of formal sleep study metrics in this population.
Practical guidance for parents: if you are concerned about your child’s breathing during sleep, recording a short video on your phone of how they sleep, mouth posture, breathing sounds, any pauses or gasps, is genuinely useful clinical information. Bring it to your appointment. I regularly ask parents to do exactly this.
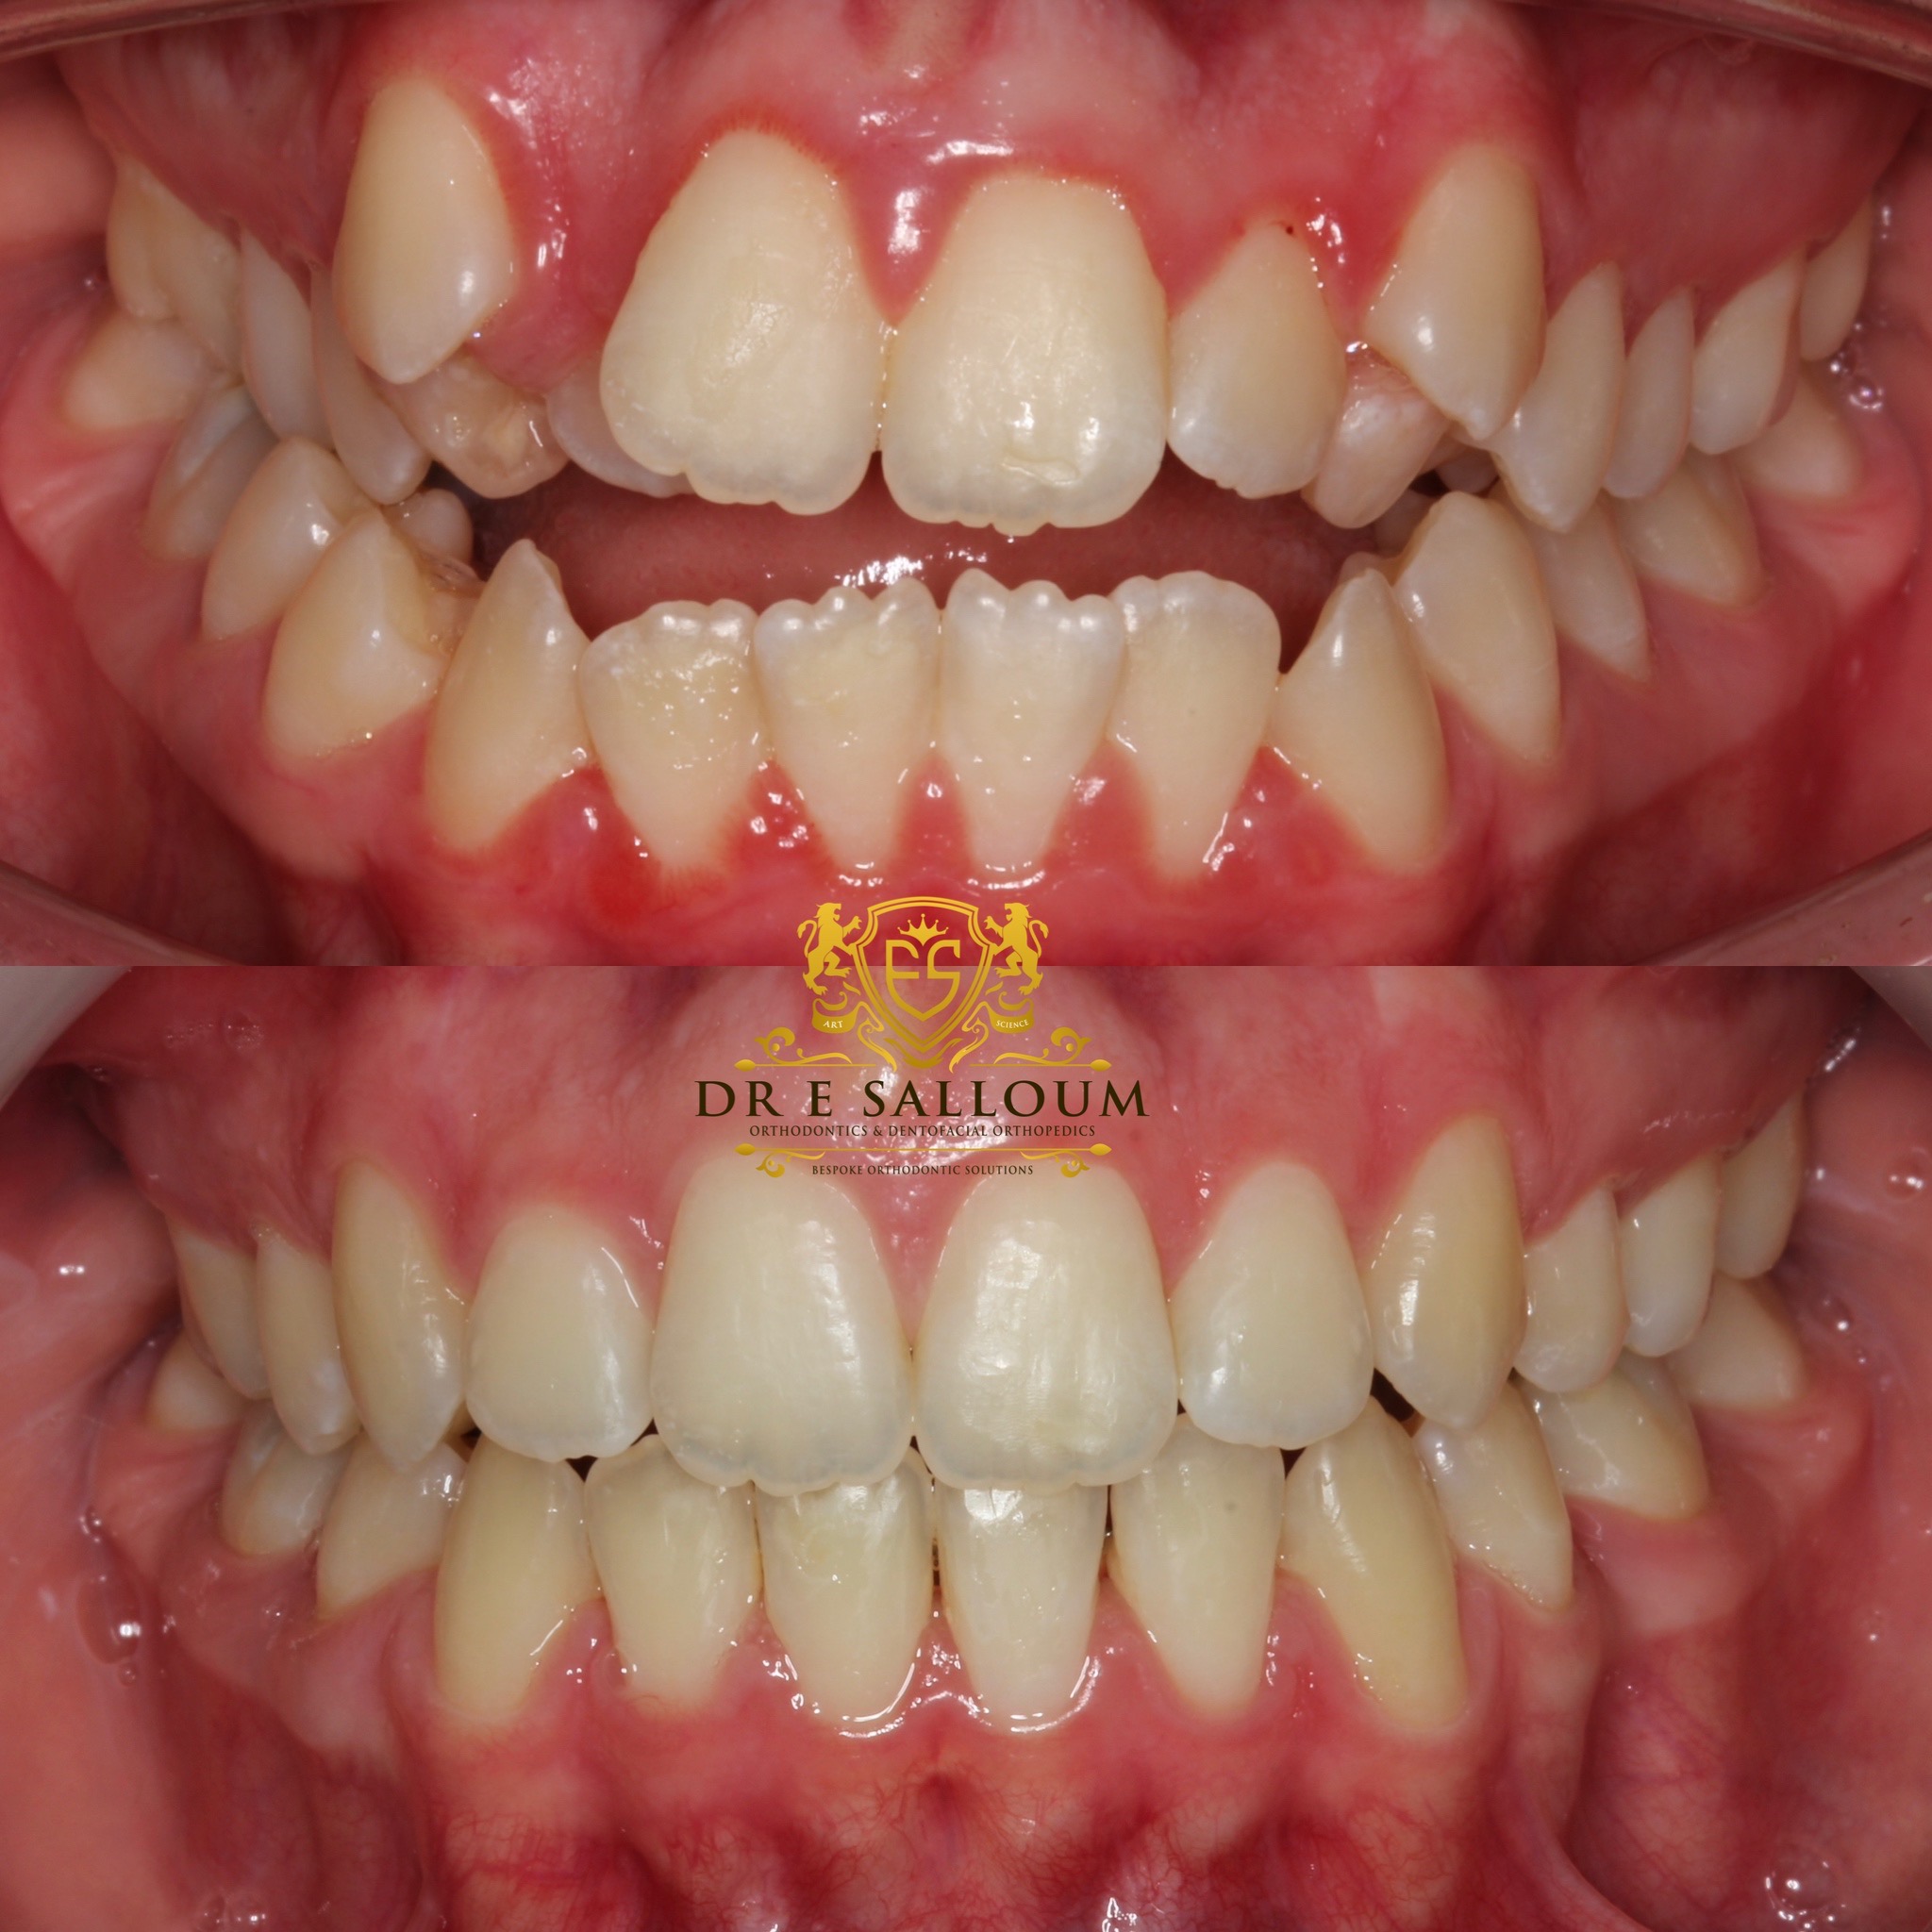
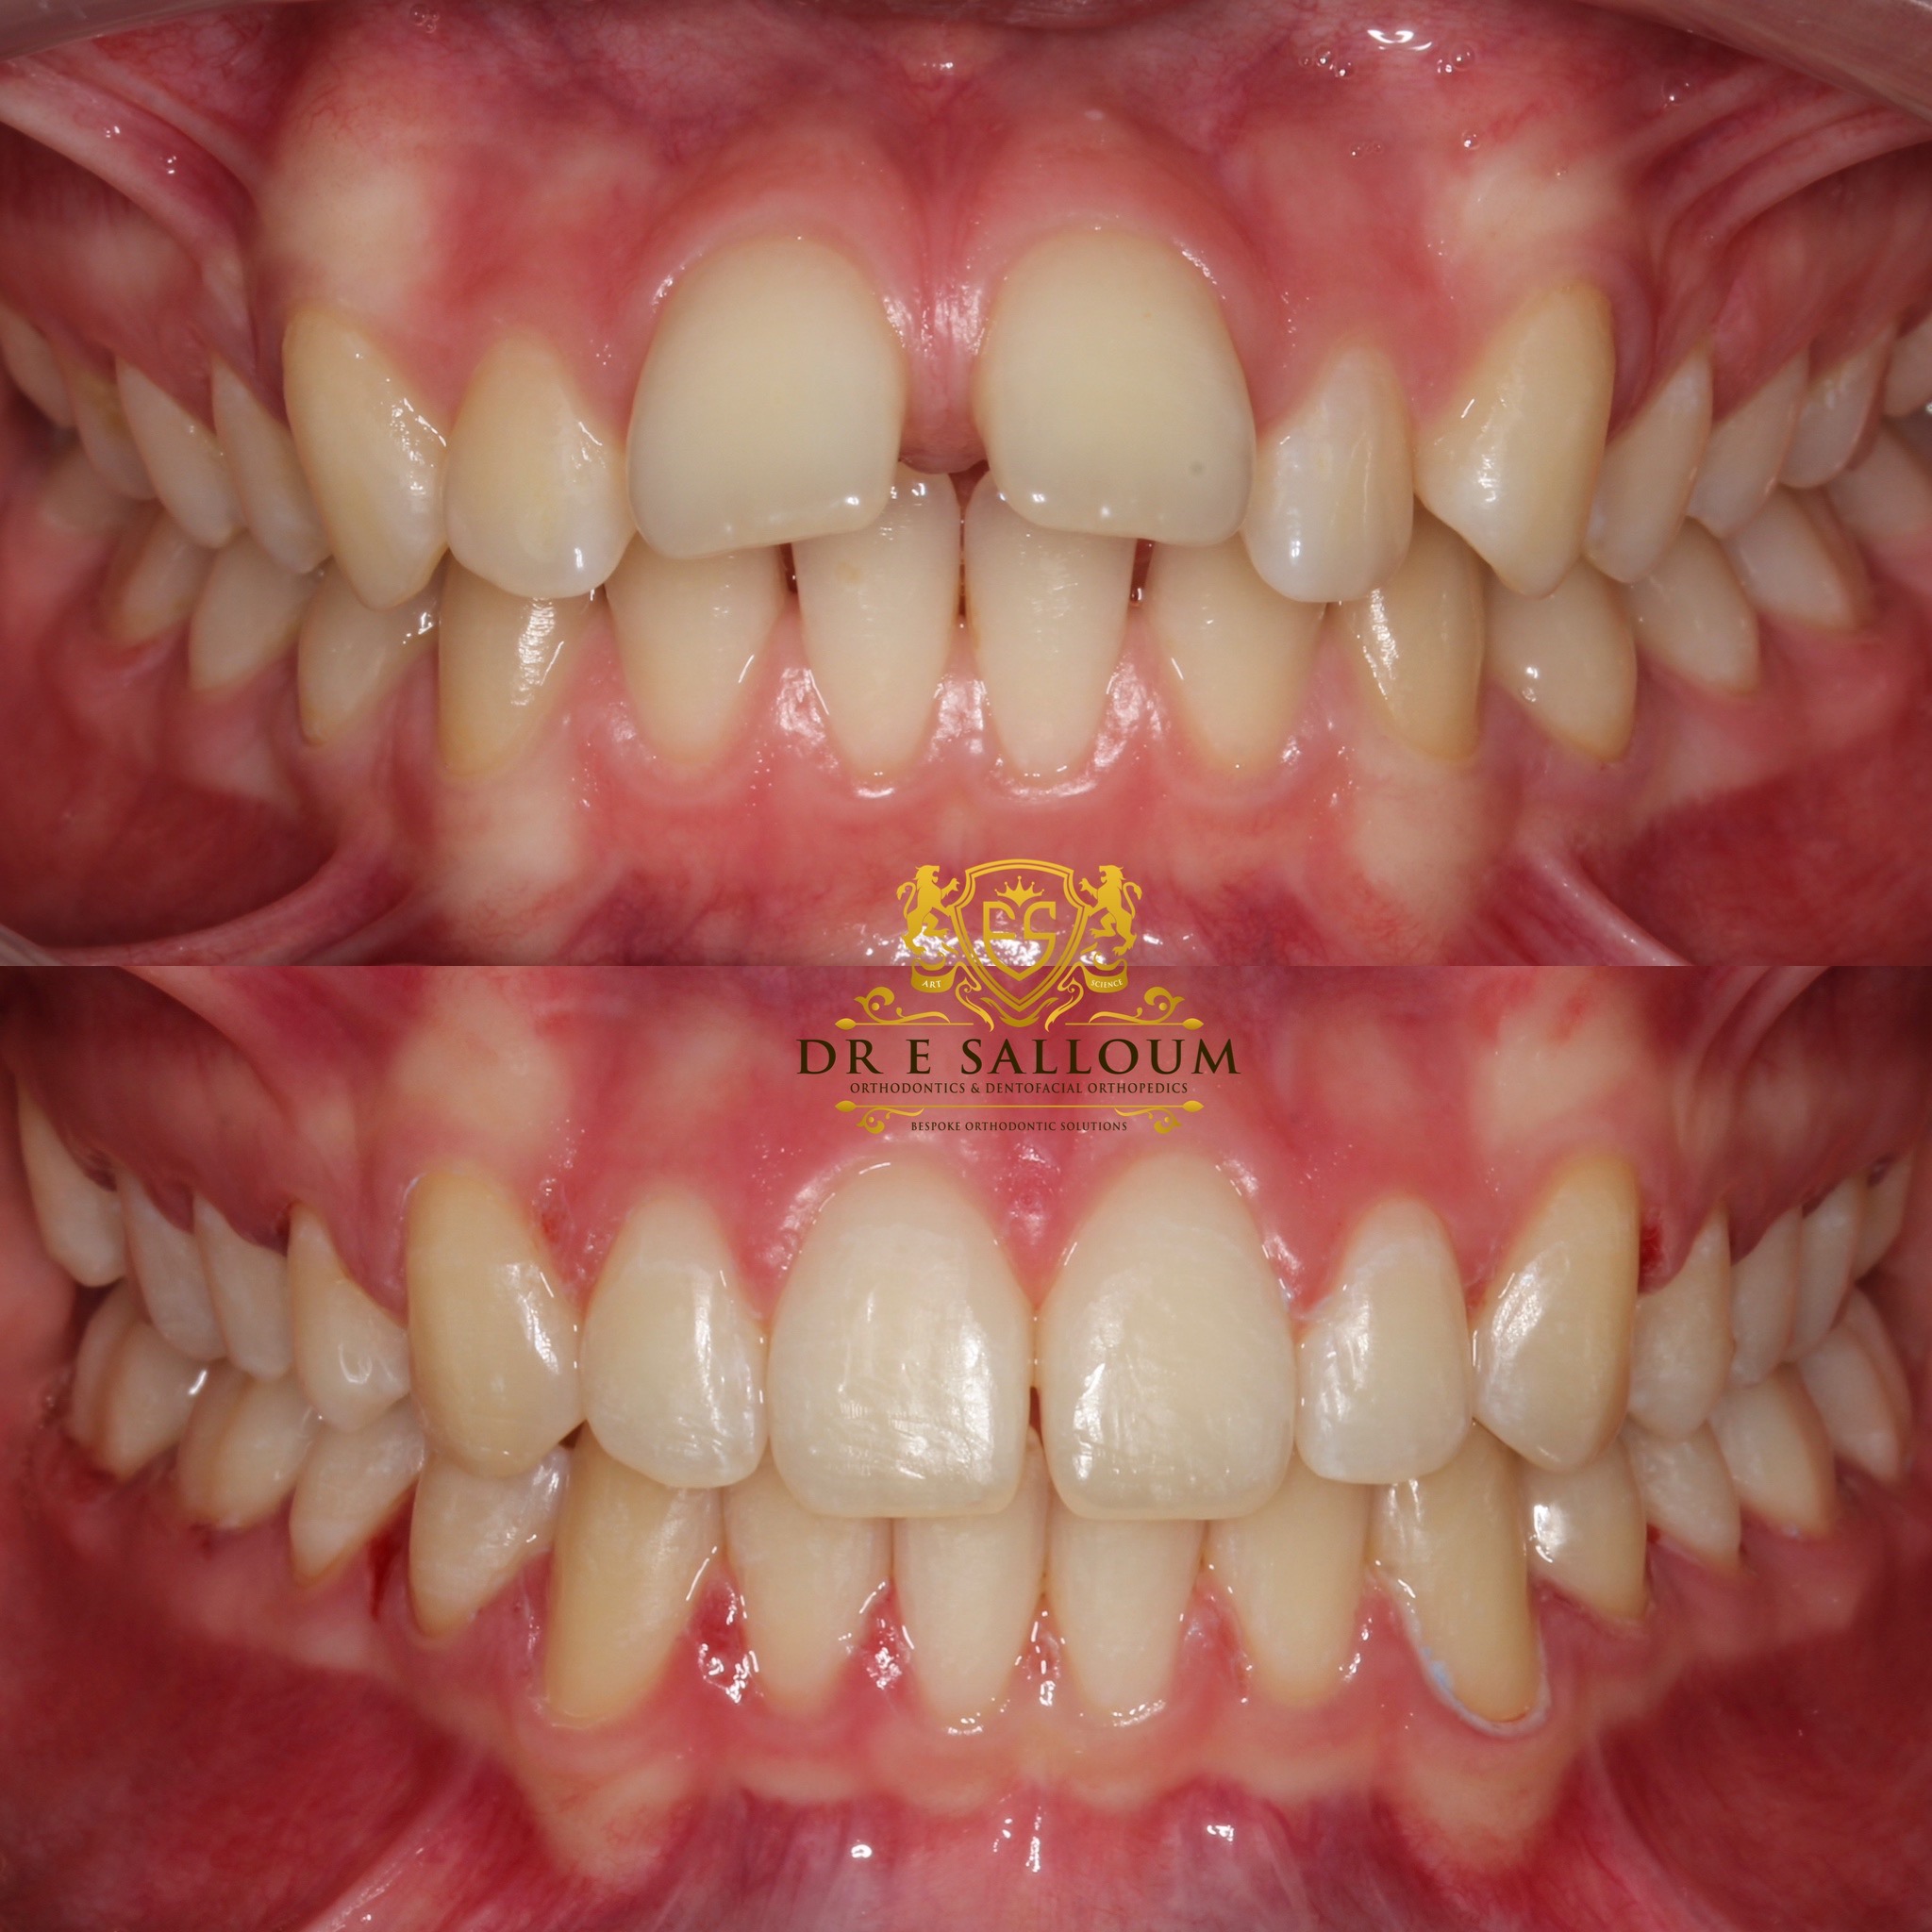
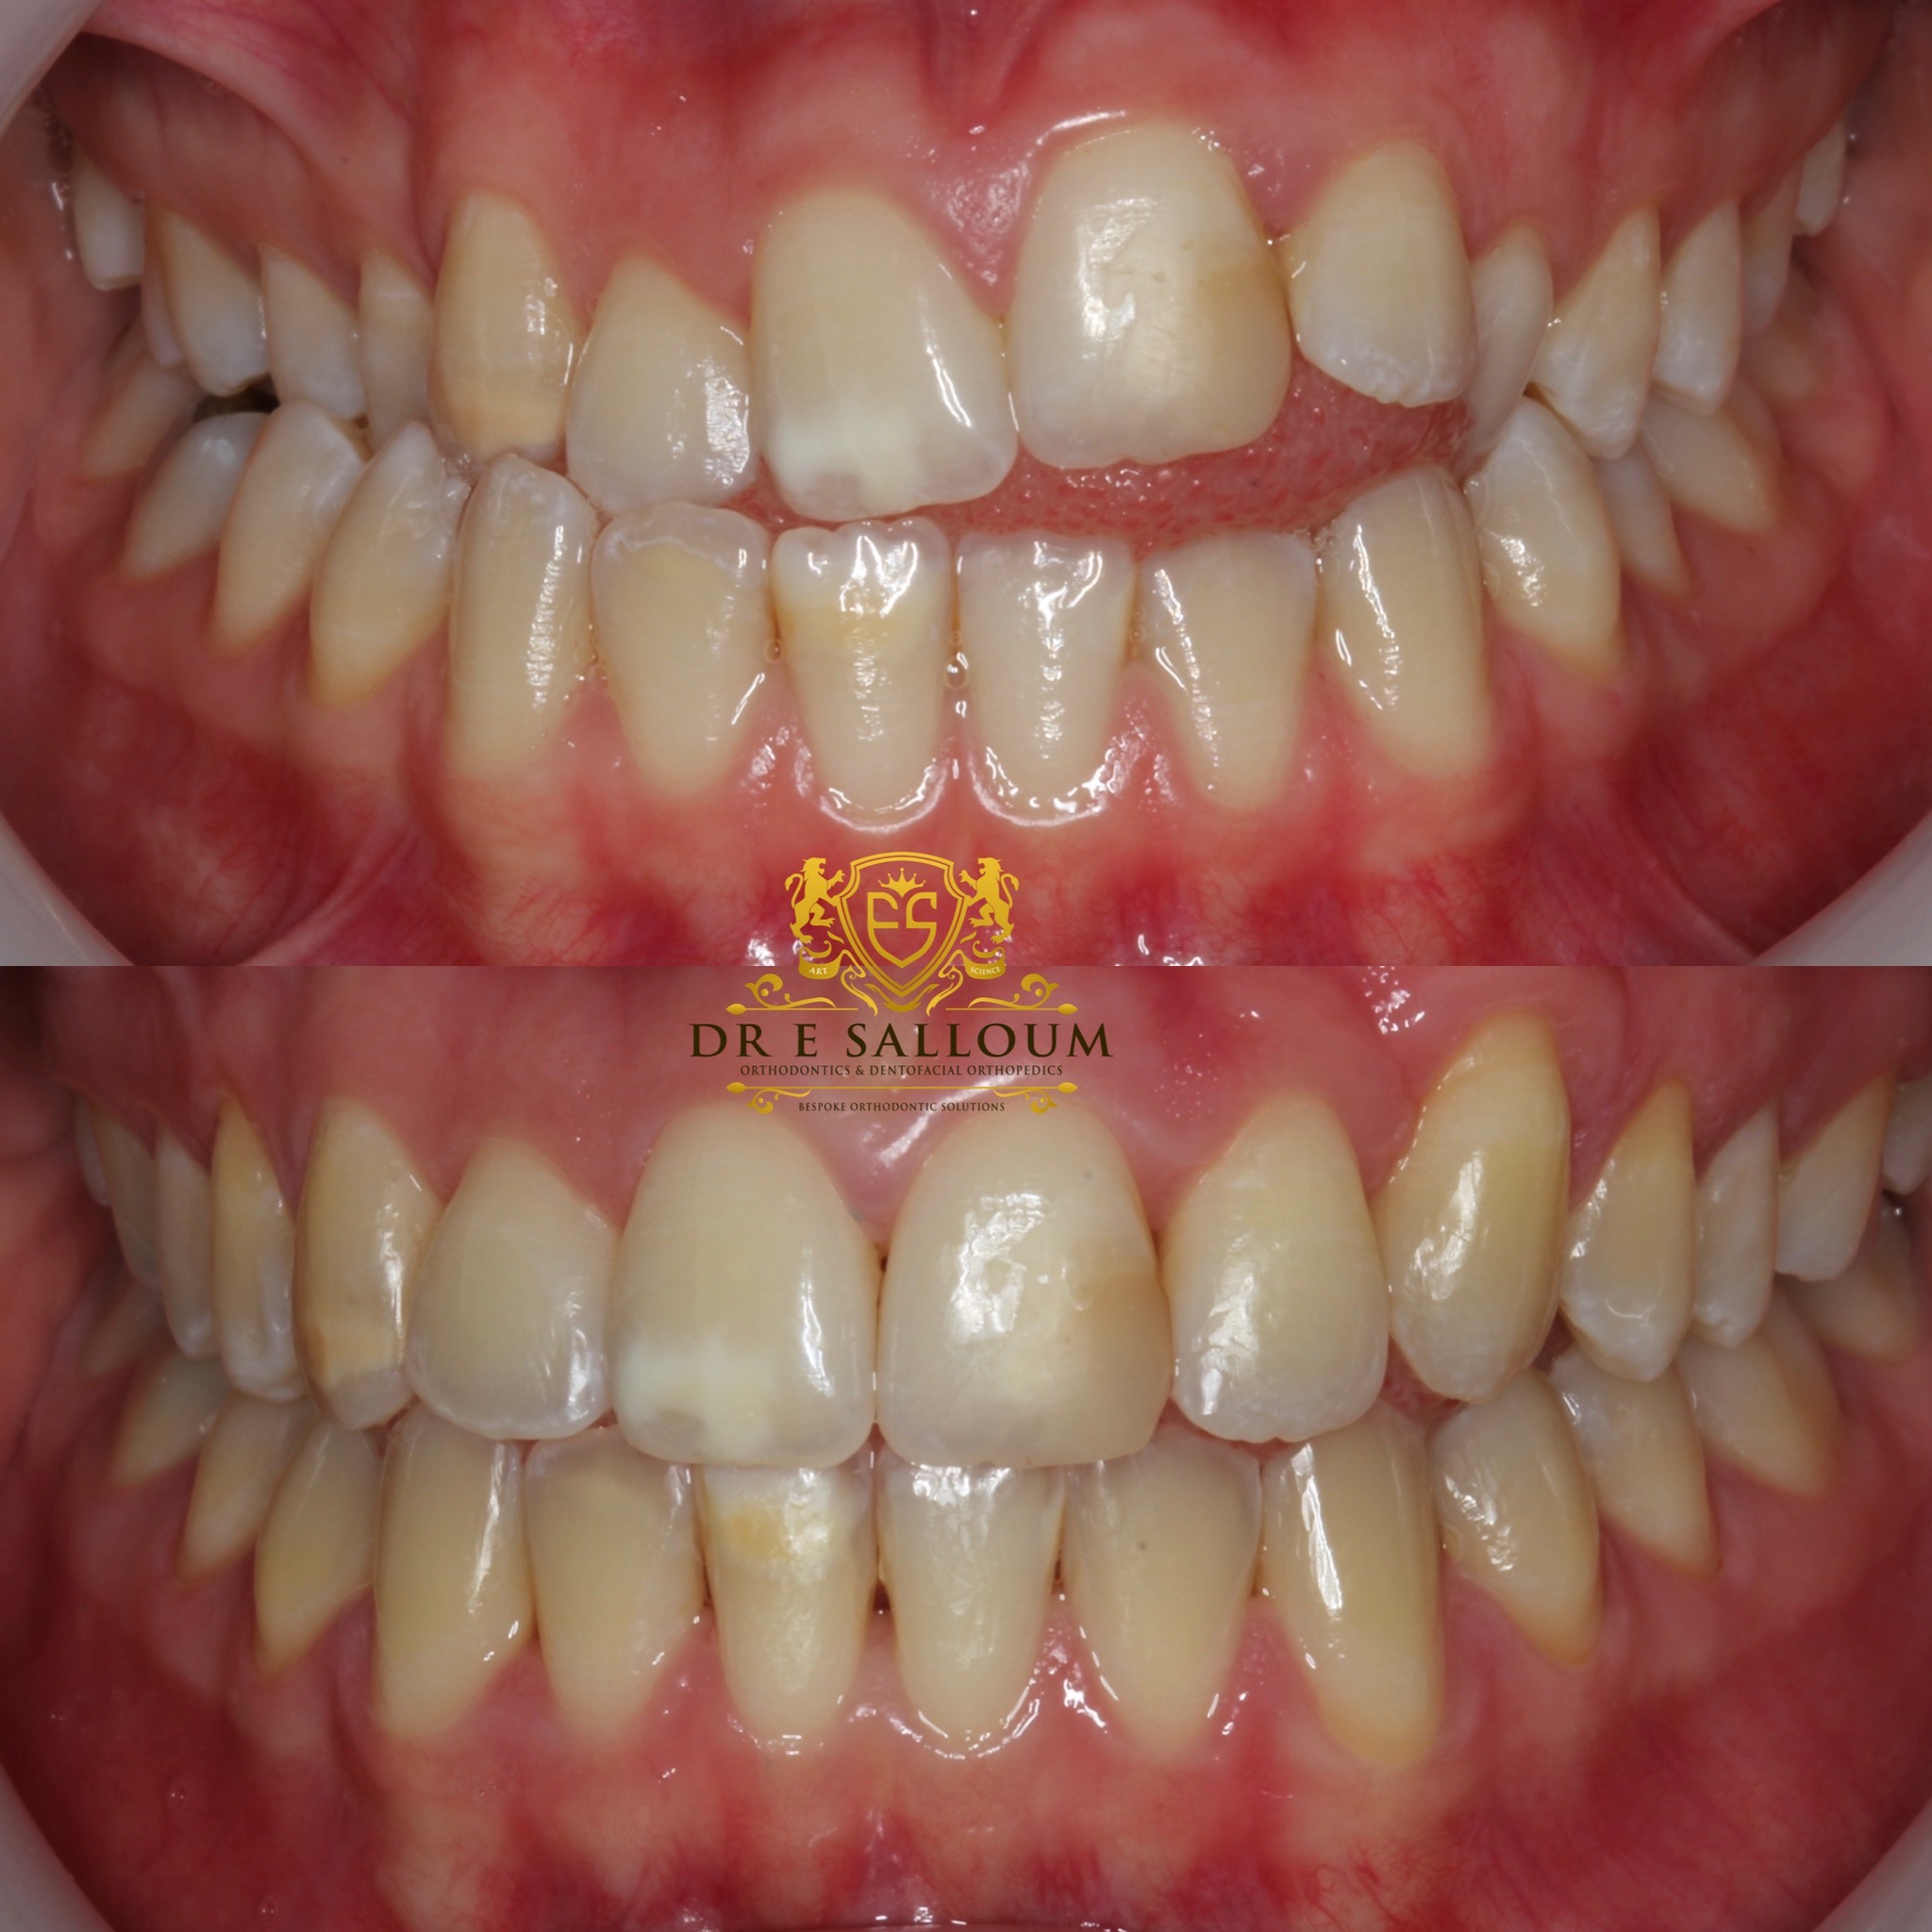
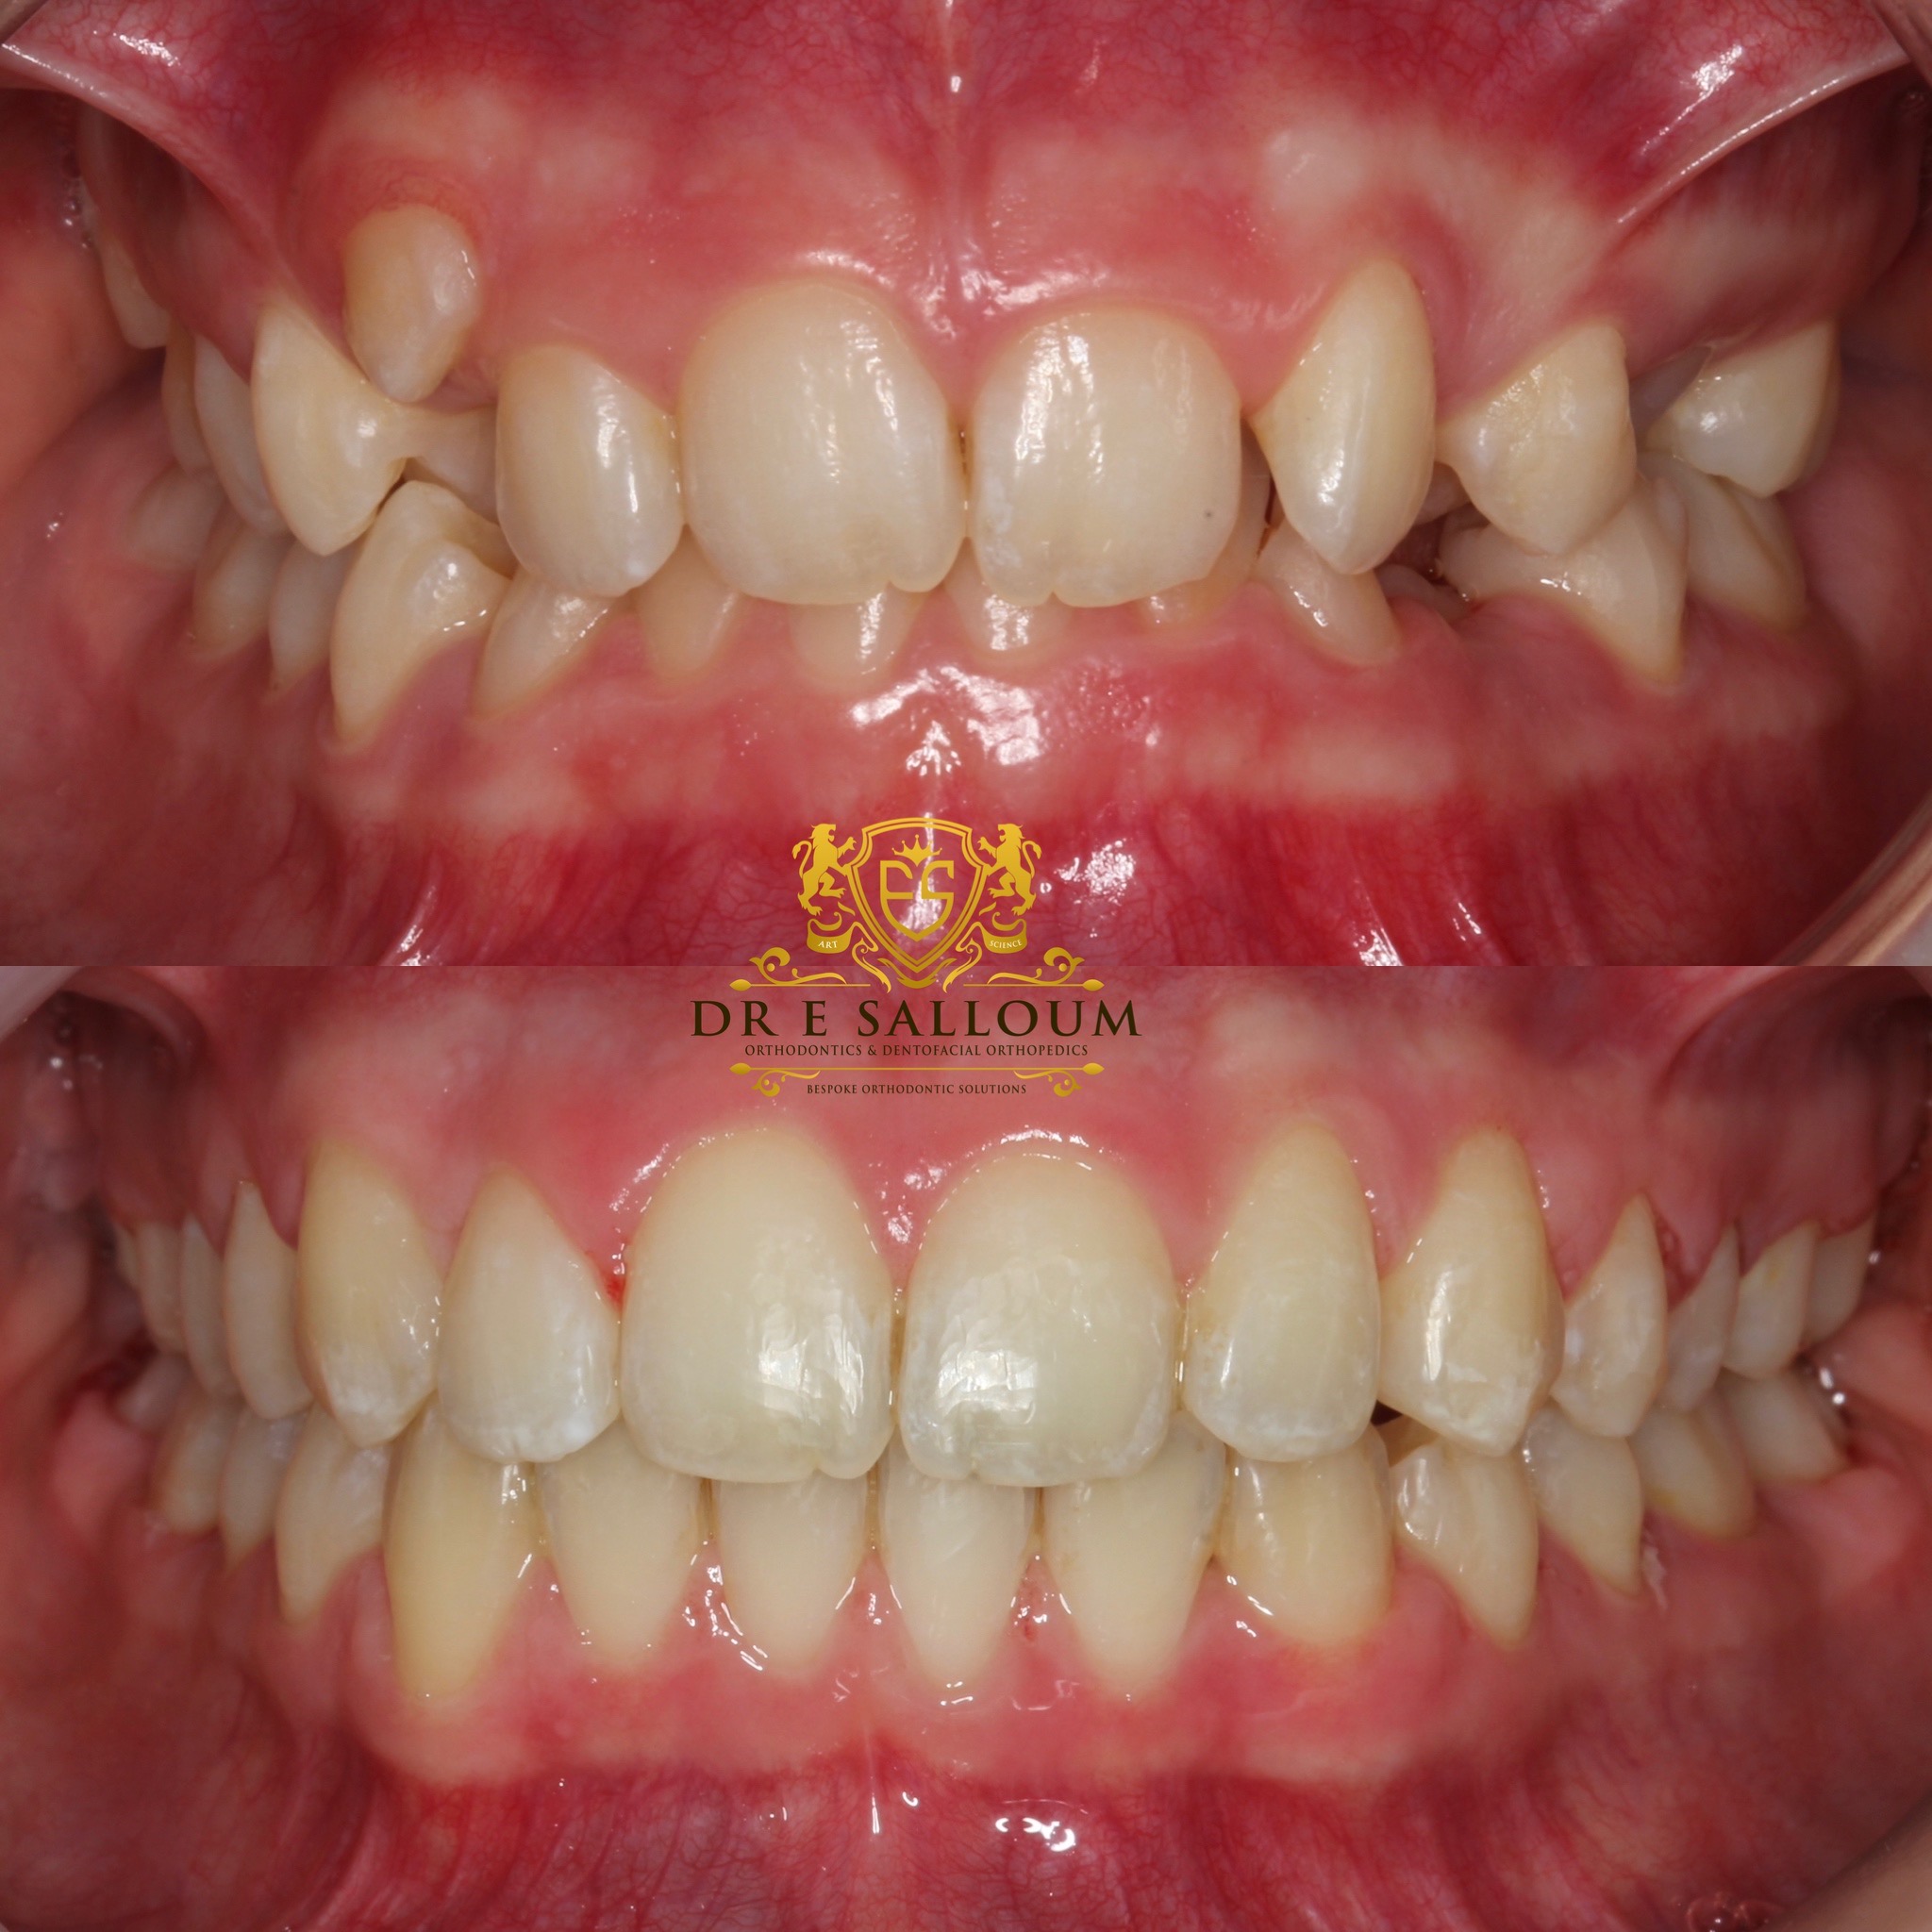
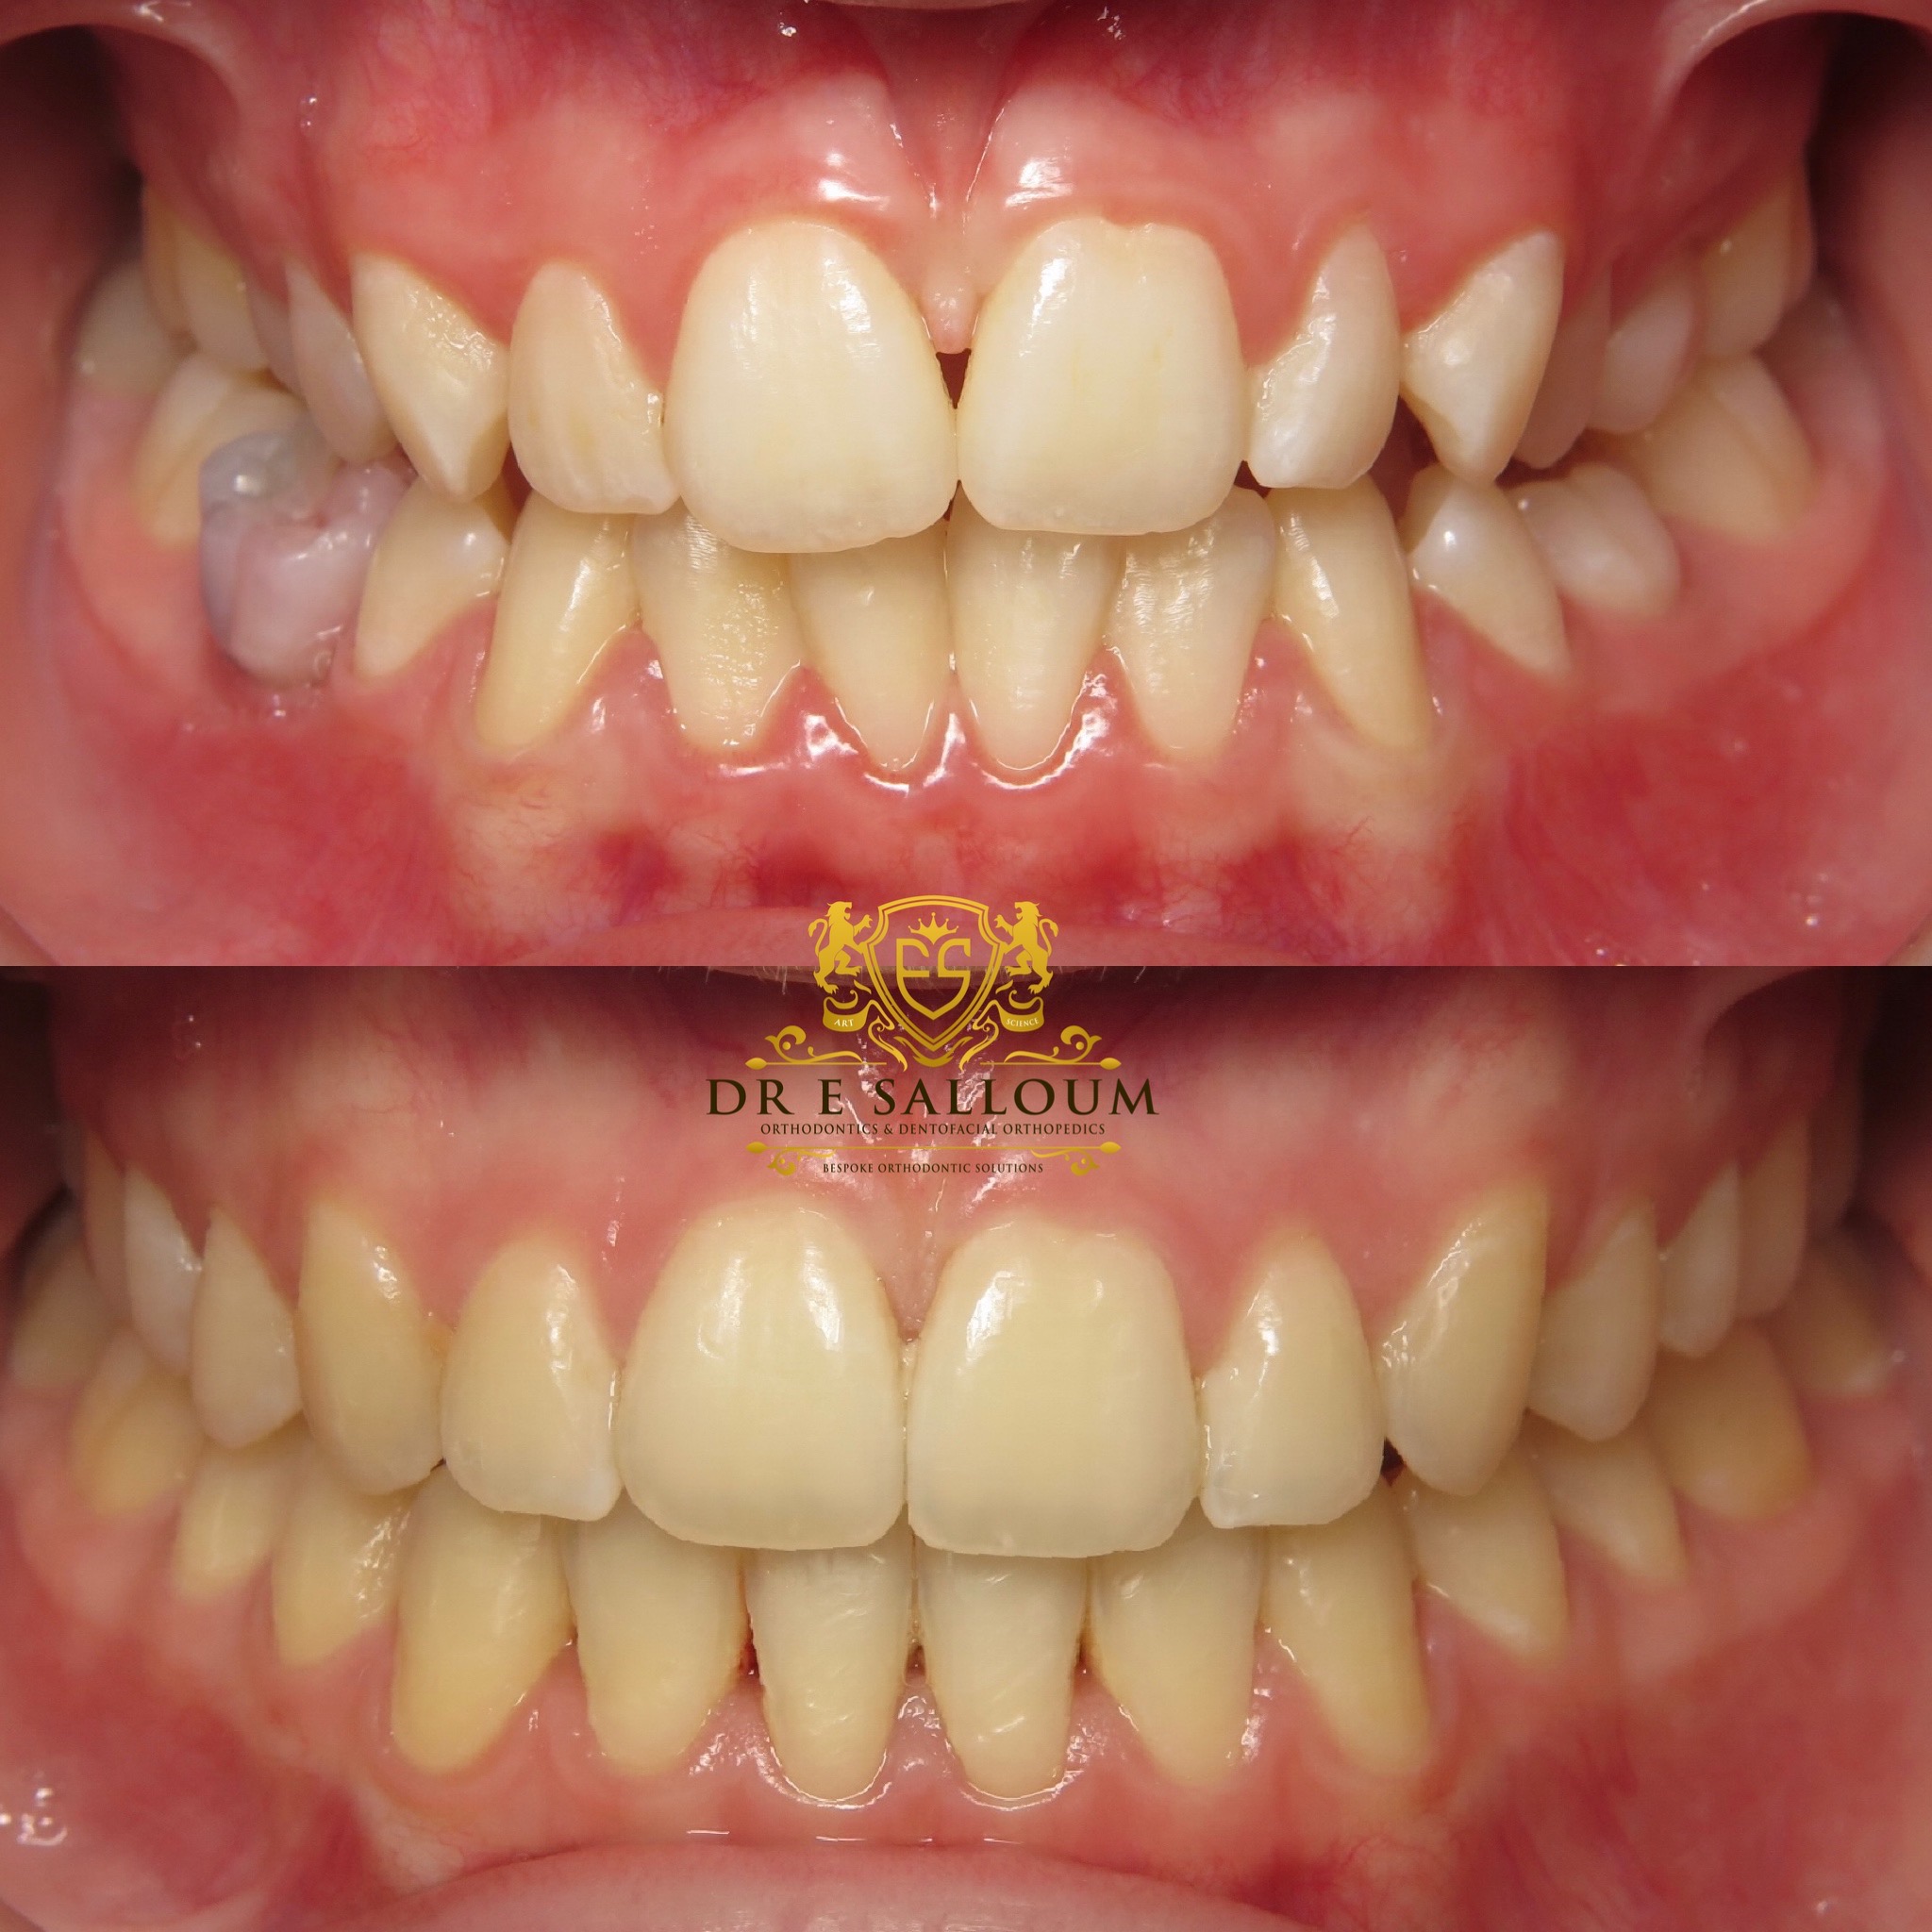
Let me be direct: there is concrete evidence, both in the published literature and from my clinical practice, that palatal expansion improves nasal airway function in children and adults. This is not a fringe claim. It is supported by clinical experience, systematic reviews and randomised controlled trials.
The mechanism is anatomical. The roof of the mouth (the palate) forms the floor of the nasal cavity. When the upper jaw is narrow, the nasal cavity above is correspondingly compressed. Expanding the palate, using a rapid palatal expander (RPE) in children, or a miniscrew-assisted rapid palatal expander (MARPE) in older adolescents and adults, widens the nasal cavity, reduces nasal airway resistance, and improves nasal airflow.
What the evidence shows:
A 2025 systematic review published in ScienceDirect found that rapid palatal expansion consistently improves nasal airflow and respiratory efficiency. The review also reported structural changes, including increased nasal base width, a wider pyriform aperture and greater nasal cavity volume.
A separate 2025 randomised controlled trial compared rapid palatal expansion (RPE) with miniscrew-assisted rapid palatal expansion (MARPE) in late adolescents and young adults. The researchers found that MARPE produced greater improvements in nasal airflow and larger reductions in nasal resistance during both inspiration and expiration.
A 2025 review published in PMC reached similar conclusions. The authors reported that MARPE can simultaneously increase nasal cavity volume, enlarge the nasopharyngeal airway and widen the alar base in adults. These findings demonstrate that the benefits of skeletal expansion are not limited to growing children.
Long-term evidence is particularly encouraging. Studies show that palatal expansion can improve nasal ventilation and help correct mouth-breathing habits. Researchers have also demonstrated that children can maintain these improvements for up to eight years after treatment, suggesting that the functional benefits are durable rather than temporary.
A 2025 PMC systematic review of rapid maxillary expansion in children specifically found improvements in sleep outcomes and oxygen saturation alongside structural airway gains in patients with SDB.
This is meaningful and clinically important evidence. I am confident in recommending palatal expansion when there is an appropriate clinical indication, a narrow arch, high vaulted palate, nasal obstruction related to maxillary constriction, or documented mouth breathing, because the evidence supports it.
I want to be equally clear about the limits, because honest communication matters as much as enthusiasm.
Palatal expansion is not a cure for obstructive sleep apnoea. It is not a substitute for an ENT assessment when enlarged tonsils or adenoids are contributing to obstruction. It will not correct a soft tissue airway problem, obesity-related OSA, or a neuromuscular cause of breathing difficulty. And in patients without a genuinely narrow palate, expanding the arch may produce dental and skeletal changes without meaningful airway benefit.
Orthodontists should recommend palatal expansion only when a clear clinical and anatomical indication exists, not as a general treatment for every breathing problem. appropriateness of the recommendation depends on thorough assessment, honest clinical judgement, and ideally, input from ENT and sleep medicine colleagues.
Airway-focused orthodontics, when practised ethically and collaboratively, can make a genuine contribution to a patient’s health. As an orthodontist, I can:
What I cannot do — and what no orthodontist should claim to do — is diagnose or independently treat obstructive sleep apnoea, prescribe CPAP therapy, remove obstructing tonsils and adenoids, or manage the medical complexity of sleep-disordered breathing without appropriate specialist involvement.
Sleep-disordered breathing and OSA are multifactorial conditions. Skeletal structure is one contributing factor among many, including:
Even where palatal expansion is clearly indicated and likely to improve nasal airflow, it may not be sufficient on its own. A child with a narrow palate and significantly enlarged adenoids needs both orthodontic treatment and an ENT assessment. Treating only one factor while ignoring the other is incomplete care.
In my practice, I work closely with ENT specialists, sleep physicians, paediatricians, and myofunctional therapists. When I identify signs of airway compromise in a patient — whether a child or an adult — my first step is to ensure they receive a thorough medical evaluation. Orthodontic treatment then contributes as one component of a broader, coordinated plan.
I will never recommend orthodontic expansion as a standalone treatment for OSA or position it as a replacement for the medical workup and specialist involvement that complex airway cases require. The two roles are complementary, not interchangeable.
The growing awareness of breathing-related health issues has, unfortunately, also created a market for overclaiming. Some clinics now actively market orthodontic appliances — braces, expanders, aligners — as treatments that cure or significantly reverse sleep apnoea and breathing disorders, often without any reference to medical collaboration, independent diagnosis, or the nuance of patient selection.
This is a problem, and I want patients and families to be aware of it.
Ethical orthodontic practice in this area looks like this:
Red flags to watch for:
I raise these not to be critical of the field, airway-focused orthodontics, done well, is genuinely valuable. I raise them because patients deserve to know what honest, evidence-based care looks like, so they can recognise it when they see it.
In my clinical assessments, the following findings lead me to discuss airway health with patients and families, and in many cases to recommend specialist referral:
In children:
For adults:
Can orthodontic treatment fix my child’s breathing problems? It depends on the cause. If your child has a genuinely narrow upper jaw contributing to nasal obstruction and mouth breathing, palatal expansion can make a meaningful and lasting difference to nasal airflow. But this is one factor among many. Enlarged tonsils, adenoids, nasal allergy, and other causes must also be assessed, and often treated, by ENT and medical specialists. Orthodontics contributes as part of a team, not as a standalone solution.
My child had a sleep study and it was normal. Does that mean their breathing is fine? Not necessarily, particularly in children. The British Thoracic Society guidelines recognise that standard sleep study metrics including AHI have not been validated in children, and that PSG (polysomnography) is generally not required to diagnose SDB in paediatric patients. Clinical symptoms, questionnaires, and sleep videos are legitimate and recognised diagnostic tools. If you are concerned about your child’s breathing during sleep, please raise it with me or your paediatrician, don’t assume a normal sleep study tells the full story.
Can MARPE help adults with breathing problems? Yes, the evidence for MARPE in adults is growing. Recent RCTs confirm that MARPE can significantly increase nasal airflow, reduce nasal airway resistance, and expand nasal cavity dimensions in adults with narrow arches. For adults with mild-to-moderate OSA and skeletal nasal obstruction, MARPE may be a valuable component of a multidisciplinary treatment plan. I would still recommend assessment by a sleep physician and ENT to ensure all contributing factors are properly addressed.
What’s the difference between airway-focused orthodontics and standard orthodontics? In my practice, every orthodontic assessment includes consideration of the airway, nasal breathing, and soft tissue function, these are not separate concerns. “Airway-focused orthodontics” at its best simply means practising orthodontics with awareness of how jaw structure and breathing are connected. Where I have concerns, I involve the right specialists. The difference from standard care is the level of attention given to these functional factors, not a separate category of treatment.
How do I know if expansion is right for my child? It starts with a proper clinical examination. If your child has a narrow upper arch, high vaulted palate, posterior crossbite, or signs of mouth breathing and nasal obstruction, expansion may be indicated. I will explain the clinical rationale clearly, discuss realistic expectations, and ensure the right specialist assessments are in place before we proceed.
For more on this topic and more, click here for my YouTube channel.
If you want to book your child and your self for an assessment, click here.
Back to Blog

I recommend and prescribe orthodontic treatments to my patients as if they were my own family and I value meaningful relationships based on communication, confidence and trust.

“We highly recommend Dr Erfan Sallom, he transformed our daughter's teeth and she’s extremely happy with her beautiful smile! We were looking for a Orthodontist...”

“I was very anxious about orthodontic treatment and as such delayed it for years. I had no need to be nervous with the expertise and...”
“I would really recommend anyone to Dr Erfan Salloum, my experience with Erfan was amazing. I had no issue he was very knowledgeable about his...”
“I have just finished my two year orthodontic treatment with Dr Erfan and I would highly recommend. He explained everything perfectly about the treatment plan...”