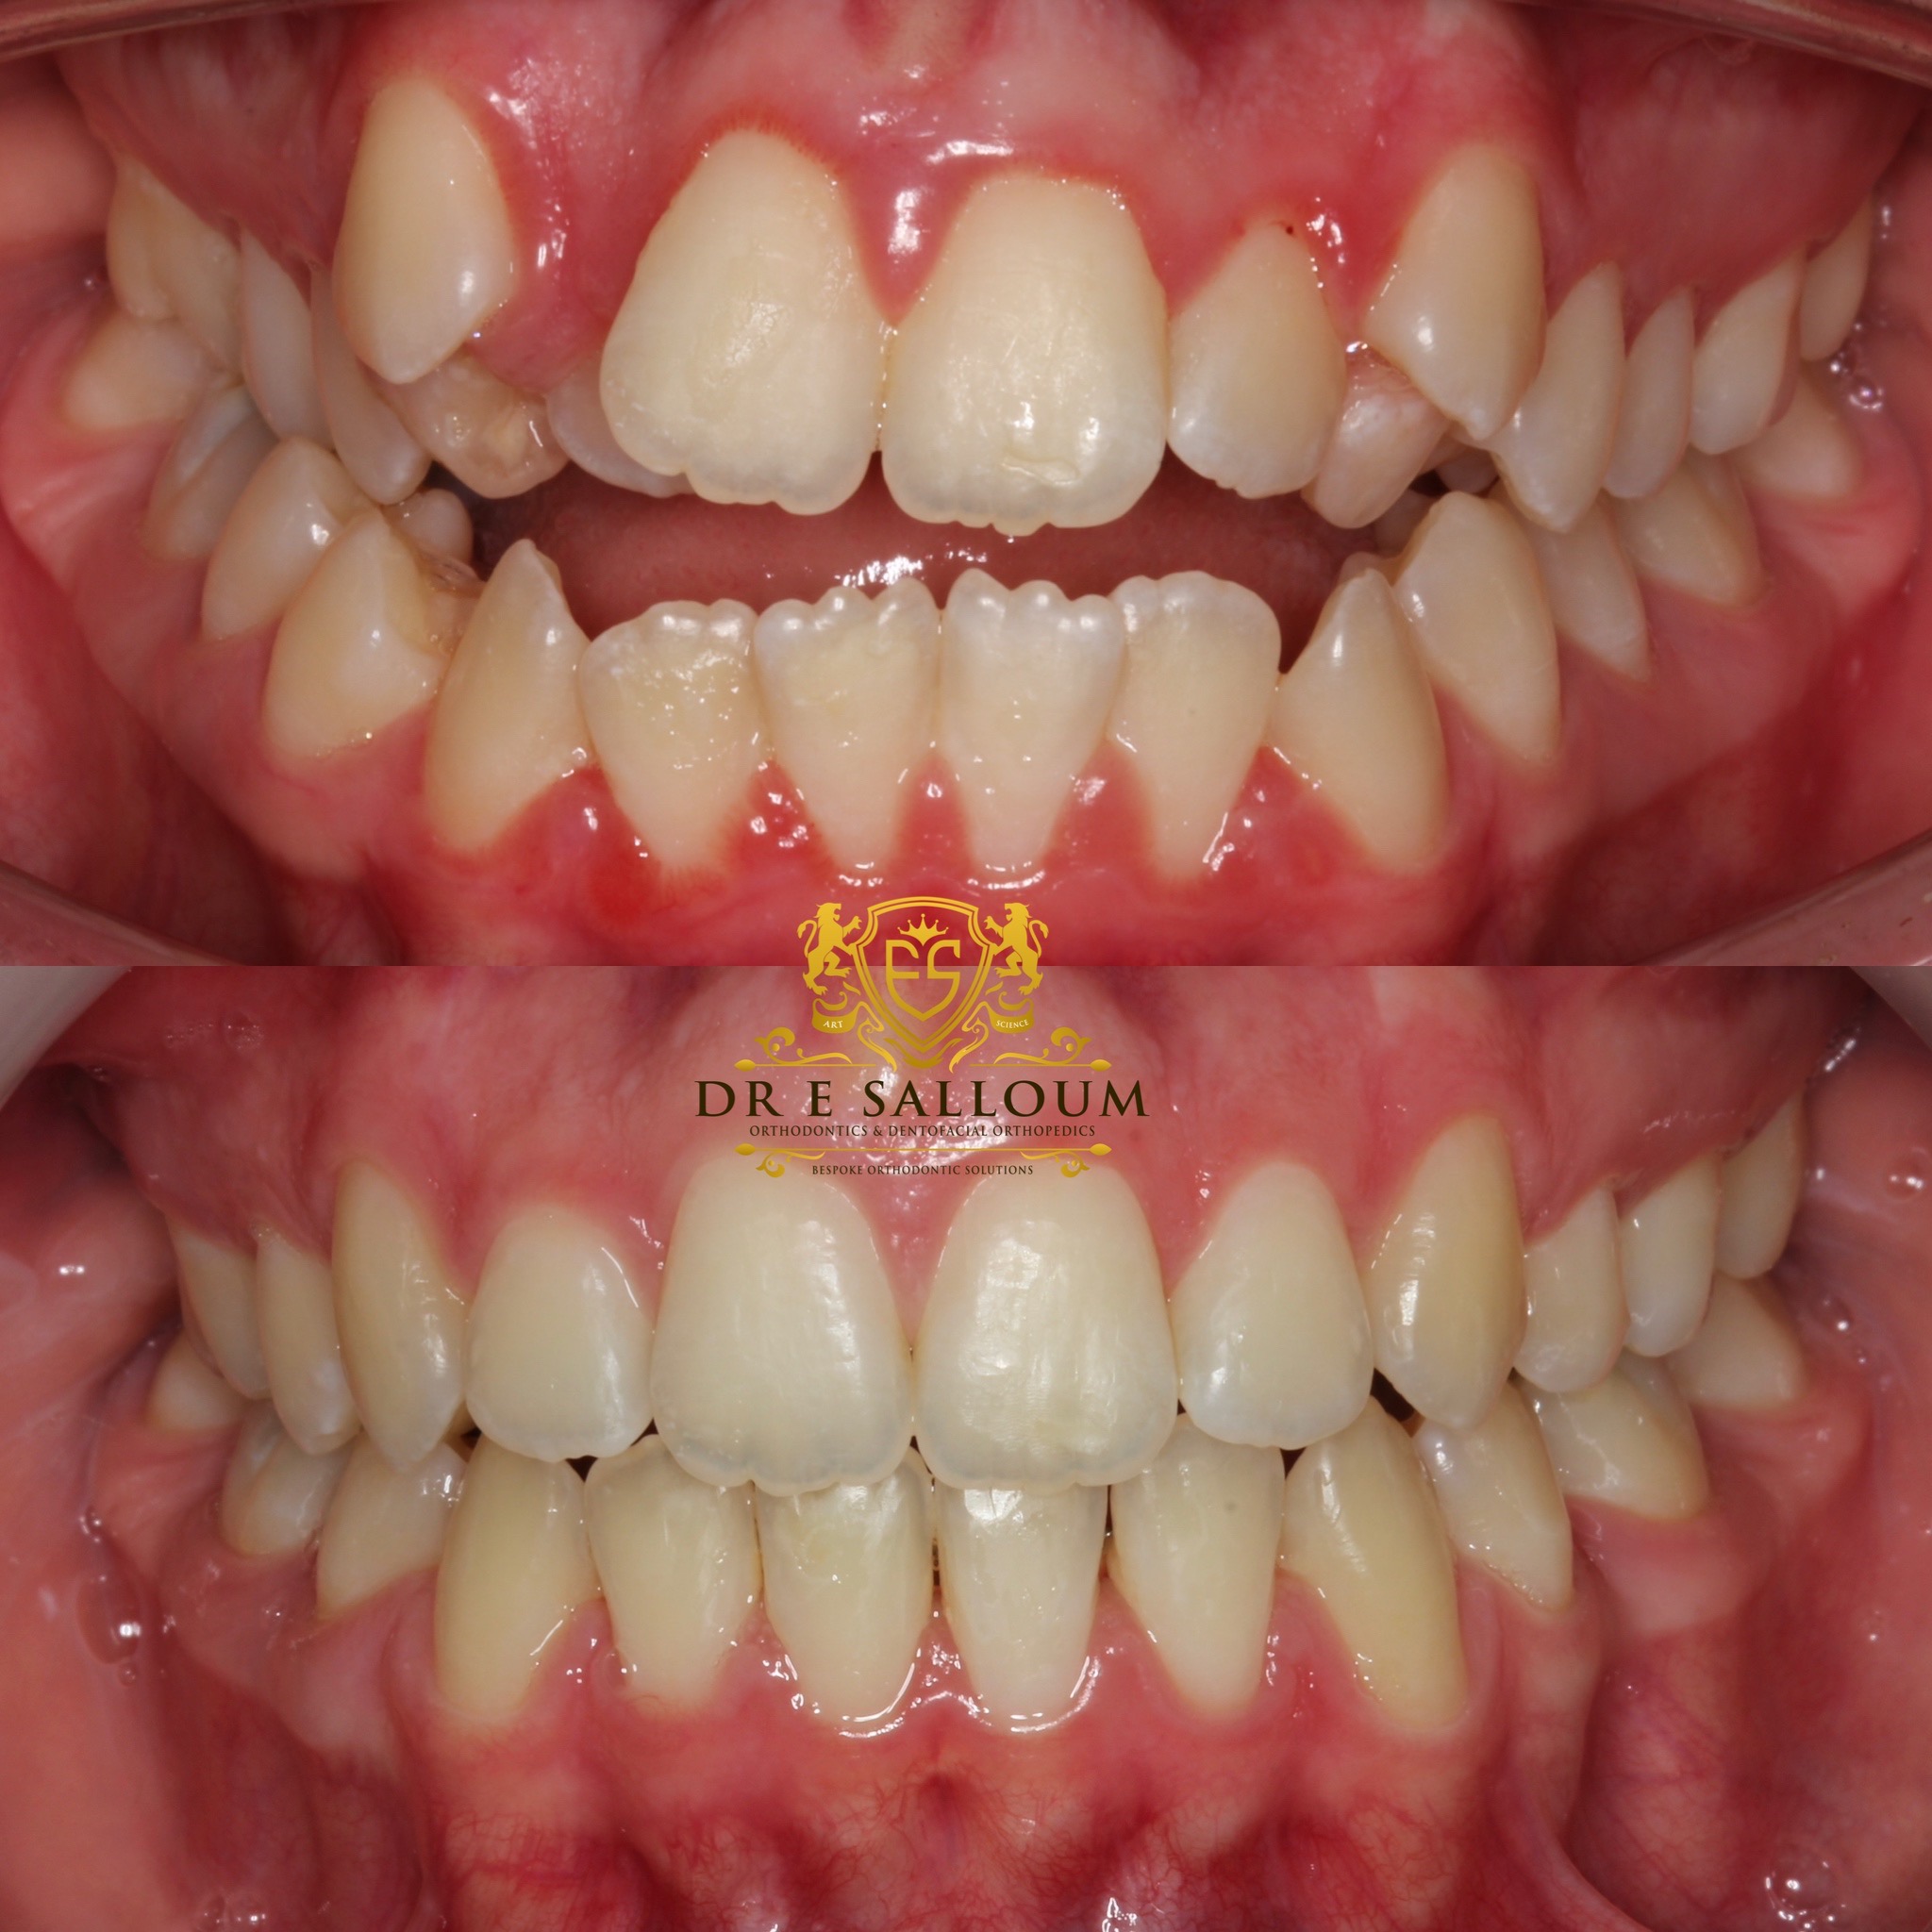
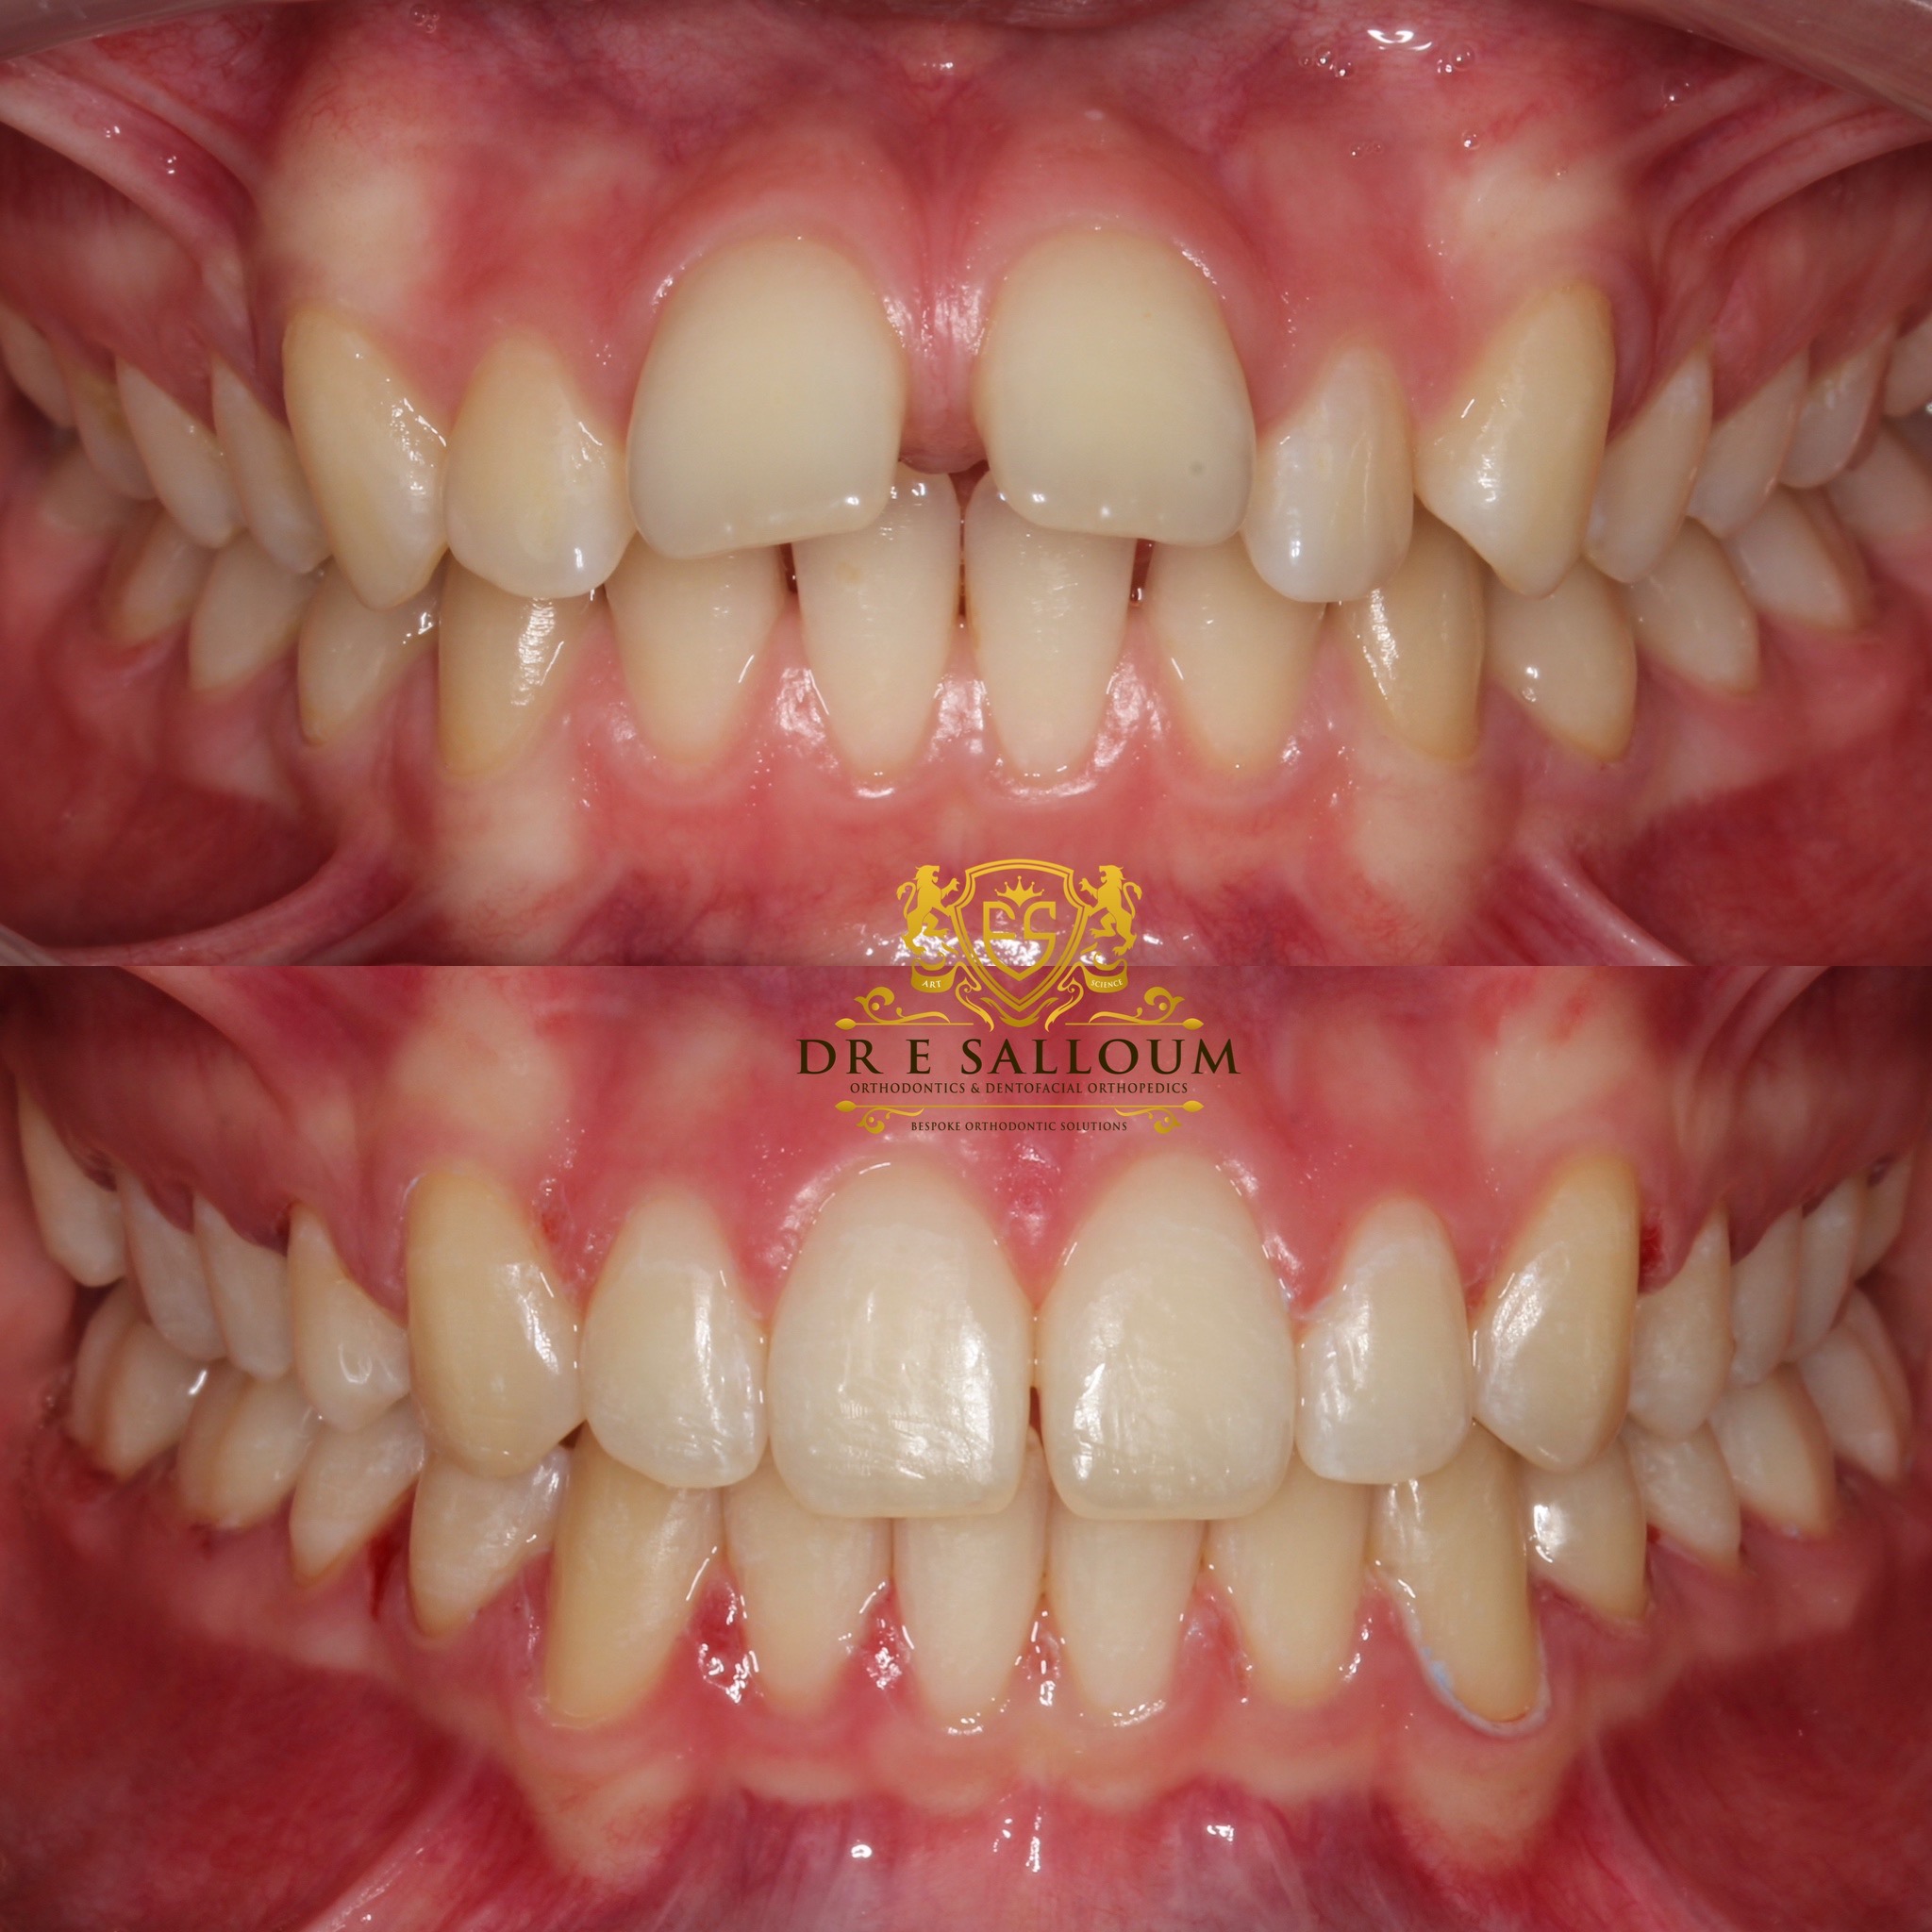
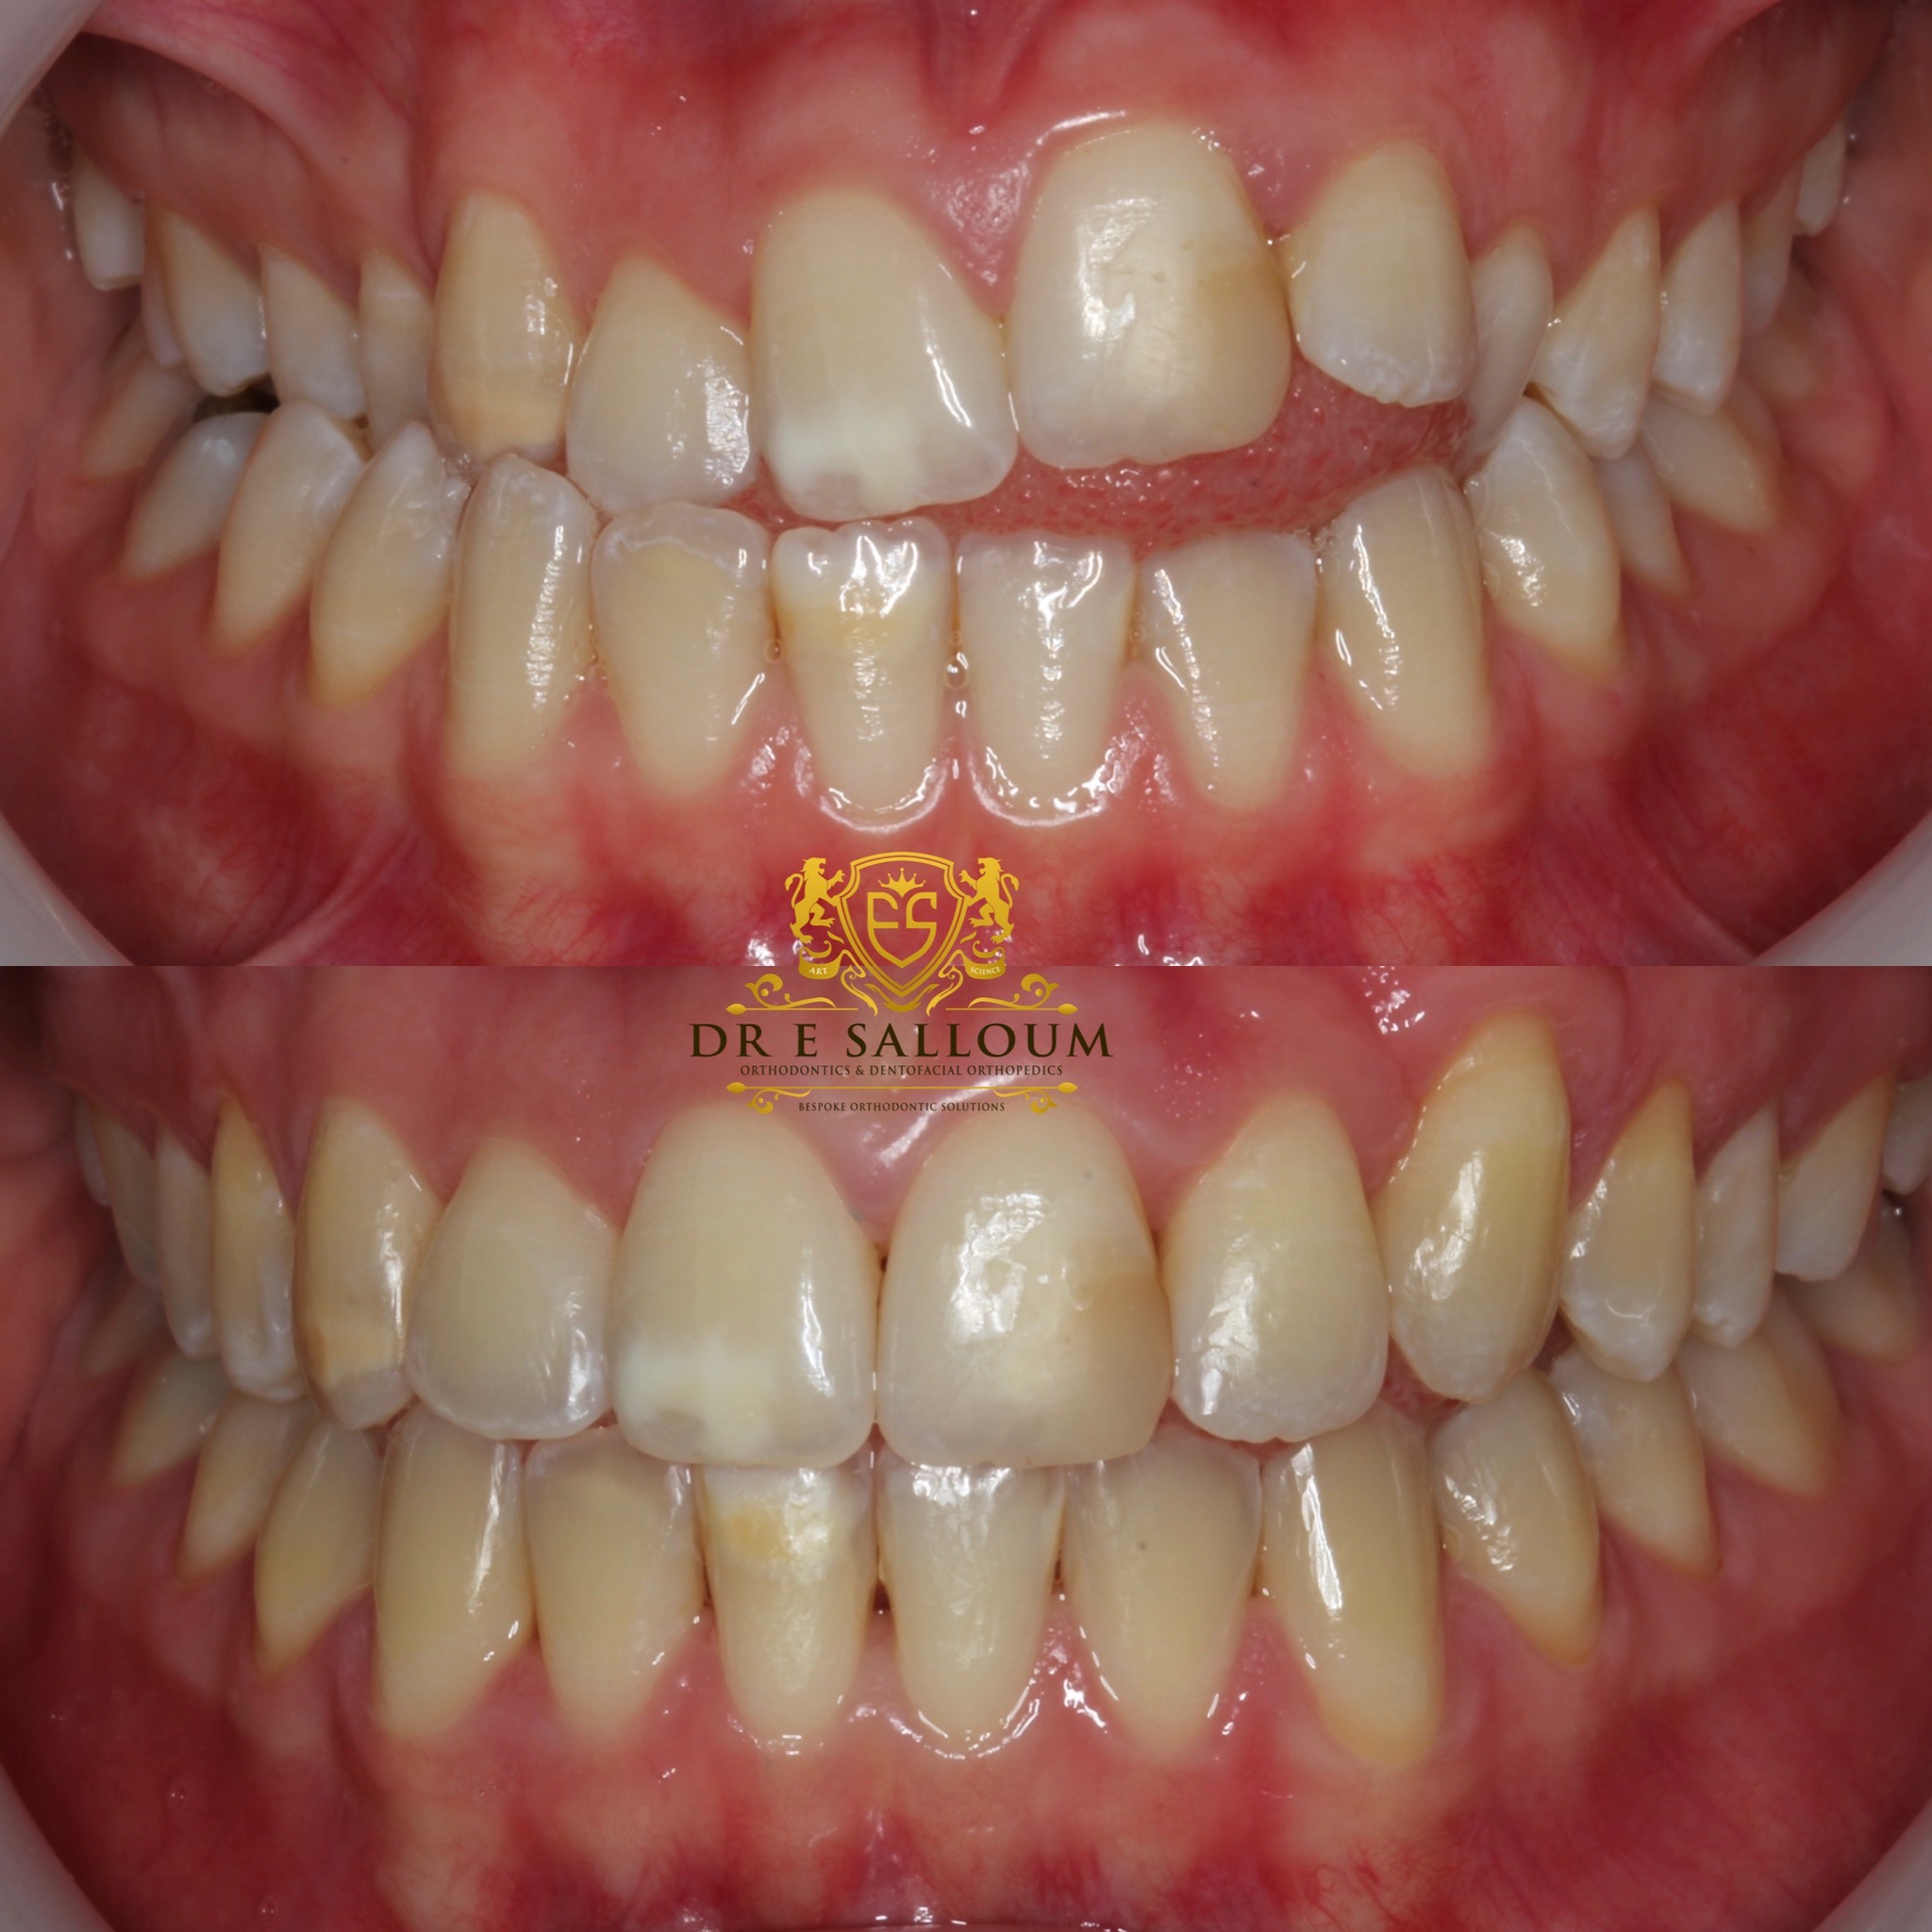
Almost every week, I answer questions about myofunctional therapy from parents researching treatment options for their children, adults concerned about relapse after previous orthodontic treatment, and patients who have read about it online and want to know whether it is really worth it
This guide reflects my honest clinical perspective, grounded in the best available evidence. I want to be upfront about something important from the start:
Myofunctional therapy is not orthodontic treatment. It is not something orthodontists perform. And it does not replace what I do.
What it is, and why I increasingly recommend it alongside my care, is the subject of this article.
Myofunctional therapy (formally called orofacial myofunctional therapy, or OMT) is a structured neuromuscular rehabilitation programme that retrains the muscles of the face, tongue, lips, and throat. It is typically delivered by a certified orofacial myofunctional therapist (OMT), a specialist who may be a speech-language pathologist, dental hygienist, or other allied health professional with advanced post-graduate training in orofacial function.
Myofunctional therapy targets the habits that interfere with healthy dental and facial development:
Think of it as physiotherapy for the orofacial muscles. Just as a physiotherapist rehabilitates an injured knee through targeted exercises, a myofunctional therapist retrains dysfunctional muscle patterns through structured daily exercises and habit modification, typically over 6–12 months.
I cannot emphasise this clearly enough, because confusion on this point leads to unrealistic expectations — and sometimes to patients avoiding or delaying the orthodontic care they actually need.
Orthodontic treatment — braces, clear aligners, expanders, functional appliances — directly moves teeth, corrects skeletal discrepancies, and guides jaw development using mechanical forces. Specialist orthodontists diagnose these problems and provide the orthodontic treatment needed to correct them.
Myofunctional therapy— does not move teeth, expand the dental arches, correct jaw discrepancies or replace braces and clear aligners.
What myofunctional therapy does is address the underlying functional environment — the muscle habits and breathing patterns that either support or undermine orthodontic treatment. In this role, it is a valuable adjunct: a complementary therapy that works alongside orthodontic treatment, not instead of it.
A patient who pursues myofunctional therapy alone, while declining orthodontic treatment for a significant malocclusion, is not receiving the care they need. Conversely, a patient who completes orthodontic treatment without addressing underlying tongue thrust or mouth breathing is at significant risk of relapse. The two work best together.
Certified orofacial myofunctional therapists deliver myofunctional therapy by retraining the muscles of the face, lips and tongue rather than using orthodontic mechanics.This is an important distinction for patients to understand: your orthodontist diagnoses and treats the structural problem; the myofunctional therapist addresses the functional problem. Both are necessary; neither replaces the other.
When I refer patients for myofunctional therapy, I look for therapists certified through recognised professional bodies:
Not every speech therapist or dental hygienist is trained in OMT. Certification from one of these bodies demonstrates that a therapist has completed specialist post-graduate training in orofacial function, assessment, and rehabilitation. I encourage patients to ask any prospective therapist about their credentials before beginning a programme.
The most effective care model is one where the myofunctional therapist and I communicate directly — sharing records, aligning on treatment goals, and timing interventions strategically. This coordinated approach is what the evidence consistently supports.
From an orthodontic standpoint, the ages of 6–12 represent the period of greatest skeletal adaptability. This is when early orthodontic interventions — palatal expanders, functional appliances, growth modification — have the most potential to influence jaw development. But these interventions work in an environment shaped by muscle forces that are active 24 hours a day.
A child who mouth breathes exerts significantly less tongue pressure on the palate — which means the lateral expansion I achieve with an expander may not be fully maintained once the appliance is removed. A child with tongue thrust exerts several hundred grams of force against the front teeth with every swallow. No retainer can fully counteract that if the habit is never corrected.
This is why I increasingly view myofunctional therapy not an important companion to early orthodontic treatment — particularly for patients presenting with open bite, Class II malocclusion, or signs of disordered breathing.
A 2025 systematic review in the Bharati Vidyapeeth Journal of Dentistry (analysing 41 studies from 1990–2024) confirmed that combining myofunctional intervention with orthodontic treatment consistently improved skeletal and dento-alveolar outcomes in Class II cases. A 2024 scoping review in the European Journal of Orthodontics examining studies from 1997–2024 found that myofunctional therapy had a measurable positive role in orthodontic management outcomes — particularly when initiated during the growth phase.
In my practice, I typically refer patients for myofunctional therapy at one of three points:
Before orthodontic treatment begins — to establish correct tongue posture and nasal breathing, so the functional environment is as supportive as possible from the start. This is particularly valuable for younger children (ages 5–8) before active orthodontic intervention.
Concurrent with orthodontic treatment — when a patient is already in active treatment and I identify persistent myofunctional habits that are working against my appliances.
After orthodontic treatment — to address the functional causes of any relapse risk, or when relapse has already begun and I need to understand why.
One of the hardest conversations in orthodontics is explaining to a patient that their result has relapsed — that the open bite has returned, the front teeth have spaced again, or the crowding has come back. Patients often assume this is a retention failure. In many cases, it is a functional failure.
Relapse is frequently a myofunctional problem. If a patient completes orthodontic treatment still mouth breathing, still swallowing with a tongue thrust, or still with habitually low tongue posture, those forces will gradually recreate the original problem. The teeth do not “remember” their corrected position — they respond to the forces acting on them, moment to moment, day after day.
A 2024 meta-analysis on open bite management confirmed this directly: concomitant myofunctional therapy significantly reduces relapse rates following orthodontic treatment for anterior open bite. In my clinical experience, this finding resonates strongly. Open bite correction without myofunctional rehabilitation is one of the highest-risk scenarios for relapse I encounter.
This dynamic is especially significant in:
The evidence is clear: correcting the bite without correcting the function is treating the symptom, not the cause.
As a clinician, I have a responsibility to present the evidence fairly — including its limitations. Myofunctional therapy is a field where enthusiasm sometimes runs ahead of the science, and I want parents and patients to have an accurate picture.
Adjunct to Orthodontic Treatment The combined evidence from 2024–2025 systematic reviews supports OMT as an effective adjunct. A 2024 study published in PMC found patients who combined myofunctional therapy with orthodontic treatment showed a greater reduction in post-treatment PAR scores than those receiving orthodontic treatment alone — a standardised measure of occlusal improvement.
Obstructive Sleep Apnoea (OSA) — Both Children and Adults This is arguably where myofunctional therapy now has its strongest clinical trial evidence. A 2026 overview and re-analysis of systematic reviews in the Journal of Sleep Research (Pisoni et al.) confirmed OMT is more effective than control in reducing OSA severity and daytime sleepiness. Meta-analysis data shows the mean apnoea-hypopnoea index (AHI) dropping from 28.0/h to 18.6/h — a clinically meaningful reduction. A 2025 systematic review and network meta-analysis in ScienceDirect further confirmed the efficacy of OMT for OSA, both as a standalone and adjunctive intervention. For children with persistent breathing issues following adenotonsillectomy, OMT has demonstrated particular value.
Tongue Thrust and Swallowing A foundational systematic review (Chamorro et al., European Journal of Orthodontics, 2014) confirmed that myofunctional therapy reliably corrects tongue thrust and improves swallowing patterns — with improvements maintained over follow-up periods when therapy is completed correctly.
My clinical position: myofunctional therapy is a valuable, evidence-supported adjunct to orthodontic treatment. It is not a substitute for it, and claims that it can replace clinical orthodontic care should be viewed with scepticism.
While the greatest developmental benefits occur during childhood growth, adults can benefit from myofunctional therapy in meaningful ways — and this is an area where recent evidence is particularly encouraging.
Sleep-Disordered Breathing and OSA A 2025–2026 overview in the Journal of Sleep Research covering 15 RCTs (473 adults, 139 children) confirmed OMT reduces AHI by approximately 50% in adults with mild-to-moderate OSA. For adult patients who cannot tolerate CPAP therapy, or who wish to reduce dependence on mandibular advancement devices, OMT is now a legitimate adjunctive option endorsed by sleep medicine literature. A 2025 RCT also demonstrated measurable improvements in hyoid bone position and sleep indices in adults with mild-to-moderate OSA following an 8-week OMT programme.
Relapse Prevention After Adult Orthodontic Treatment Adult patients who have completed orthodontic treatment but retain tongue thrust, mouth breathing, or lip incompetence face elevated relapse risk. I regularly recommend an OMT assessment for adult patients experiencing unexplained shifting after treatment — the underlying functional cause is often identifiable and correctable.
Temporomandibular Disorders (TMD) A 2025 pilot study in PMC found OMT significantly reduced pain and improved function in adults with myogenous TMD (jaw muscle-related pain and dysfunction). This is a promising area that warrants larger trials.
The key message for adult patients: you may not be “too old” for myofunctional therapy to help, even if significant skeletal change is no longer possible. Functional improvement — better breathing, more stable orthodontic results, reduced jaw pain — remains achievable.
I want to clarify a common source of confusion. Functional orthodontic appliances — the Twin Block, Andresen Activator, Bionator, Herbst appliance — are orthodontic devices prescribed and managed by orthodontists. They mechanically reposition the jaws and modify dentoalveolar development.
Myofunctional therapy is a neuromuscular rehabilitation programme delivered by a certified OMT. It does not apply mechanical forces to teeth or bone. It retrains the muscles.
These are complementary, not interchangeable. A child wearing a Twin Block who still swallows with a tongue thrust and mouth breathes at night is working against their appliance. Adding myofunctional therapy to that picture gives the appliance the muscle support it needs to be effective — and makes the result far more likely to last.
In my clinical assessments, certain findings lead me to discuss myofunctional therapy with patients and families. These include:
In children:
In adults:
Can myofunctional therapy replace braces or aligners? No. Myofunctional therapy cannot move teeth or correct structural jaw problems. It is an adjunct — not a replacement — for orthodontic treatment. If your child needs orthodontic intervention, OMT supports that treatment but does not substitute for it.
Who actually performs myofunctional therapy? Certified orofacial myofunctional therapists — typically speech-language pathologists or dental hygienists with specialist post-graduate training. Look for IAOM or AOMT certification. I refer patients to these specialists; as an orthodontist, OMT is not something I perform myself.
When should my child start myofunctional therapy? Ideally before or at the beginning of early orthodontic treatment — typically between ages 6 and 10. Some simplified programmes can begin as young as 4–5. I assess this on a case-by-case basis and will advise on timing as part of your child’s overall orthodontic plan.
How long does it take? Most OMT programmes run 6–12 months, with regular sessions and daily home exercises. Duration depends on severity and — critically — how consistently the patient completes their exercises at home.
Can adults benefit from myofunctional therapy? Yes, particularly for mild-to-moderate sleep apnoea, relapse prevention after adult orthodontic treatment, and jaw muscle pain (TMD). The evidence for adult OMT in OSA management is now quite strong, with meta-analyses showing AHI reductions of approximately 50% in adults.
Can myofunctional therapy help with sleep apnoea instead of CPAP? It is not a replacement for CPAP in moderate-to-severe OSA. However, the 2025–2026 evidence supports OMT as a meaningful adjunct that can reduce AHI and may improve CPAP tolerance or reduce required pressures. Any changes to OSA management should be discussed with your sleep physician.
Back to Blog

I recommend and prescribe orthodontic treatments to my patients as if they were my own family and I value meaningful relationships based on communication, confidence and trust.

“We highly recommend Dr Erfan Sallom, he transformed our daughter's teeth and she’s extremely happy with her beautiful smile! We were looking for a Orthodontist...”

“I was very anxious about orthodontic treatment and as such delayed it for years. I had no need to be nervous with the expertise and...”
“I would really recommend anyone to Dr Erfan Salloum, my experience with Erfan was amazing. I had no issue he was very knowledgeable about his...”
“I have just finished my two year orthodontic treatment with Dr Erfan and I would highly recommend. He explained everything perfectly about the treatment plan...”